
Choosing between modifiers 58, 78, and 79 can determine whether a postoperative procedure receives appropriate reimbursement, triggers a denial, or creates an incorrect global-period calculation. All three apply to certain procedures performed during an existing surgical global period, yet their requirements differ significantly. Coders must evaluate the relationship between operations, whether the second procedure was planned, and where it occurred. This guide provides real-world clinical scenarios, a 30-case decision matrix, and practical strategies to improve coding accuracy, modifier selection, claim acceptance, and denial prevention.
1. Modifier 58 vs 78 vs 79: The Global Surgery Rules That Determine Your Choice
The Medicare global surgical package includes specified preoperative, intraoperative, and postoperative services associated with a surgical procedure. Understanding the package is essential because separately billing included postoperative care can create duplicate reimbursement and compliance problems.
Under Medicare's Physician Fee Schedule, global surgery indicators commonly fall into three categories:
000: The surgical package includes the day of surgery, with no additional postoperative days.
010: The surgical package includes the procedure day and 10 following postoperative days.
090: The surgical package includes one preoperative day, the procedure day, and 90 following postoperative days.
The applicable global period depends on the particular procedure code. Coders should verify the Medicare Physician Fee Schedule indicator rather than assuming that every surgical service has a 90-day global period.
This is especially important in outpatient coding scenarios, professional fee coding, and specialty coding audits, where incorrect global assumptions can affect both code assignment and payment.
Modifier 58: Staged or related surgical procedure
Modifier 58 identifies a staged or related procedure performed by the same physician or other qualified healthcare professional during the postoperative period.
Its application generally requires at least one of these circumstances:
The subsequent procedure was prospectively planned or anticipated.
The subsequent procedure was more extensive than the original.
The procedure provided therapy following an earlier diagnostic surgical procedure.
For example, a surgeon performs an initial excision and documents that definitive reconstruction will occur during a later surgical session. When the planned reconstruction is performed during the original global period, modifier 58 may identify the separately reportable staged procedure.
The medical record should establish the clinical relationship and support the applicable condition for modifier 58.
Payment consequence: The subsequent procedure generally receives payment according to its applicable surgical payment rules, and a new postoperative period begins.
Coders should verify the operative documentation using coding audit procedures, CPT coding resources, and clinical documentation clarification.
Modifier 78: Unplanned return for a related procedure
Modifier 78 identifies an unplanned return to an operating or qualifying procedure room during the postoperative period for a procedure related to the initial surgery.
A common example is a patient who develops postoperative bleeding and requires another operation to identify and control the bleeding.
Two details are particularly important. First, the second procedure must be related to the initial procedure. Second, it must involve an actual return to an operating or qualifying procedure room.
Medicare recognizes appropriately equipped and staffed procedural environments, including certain endoscopy suites, laser suites, and cardiac catheterization suites. Ordinary bedside treatment or an office examination does not automatically meet this requirement.
Payment consequence: For procedures with a global payment breakdown, Medicare generally pays the intraoperative component of the related return procedure. The original postoperative global period continues without restarting.
Modifier 78 also applies to qualifying related procedures beyond the treatment of complications. The documented circumstances determine the appropriate classification.
Incorrect modifier assignment can affect clean claim performance, denial management, and medical billing appeals.
Modifier 79: Unrelated procedure during the postoperative period
Modifier 79 identifies a procedure that is unrelated to the original surgery but occurs during its postoperative global period.
Consider a patient recovering from right-sided orthopedic surgery who subsequently requires a separate procedure for an unrelated condition involving the left hand. If the same physician or an applicable same-specialty group physician performs the new operation, modifier 79 may identify the separate surgical service.
The fact that a procedure involves another body part helps establish its circumstances but does not independently prove that it is unrelated. The underlying diagnosis, medical record, and treatment purpose must support the distinction.
Payment consequence: The unrelated procedure is considered under its own payment and global surgery rules, and a new postoperative period begins for the subsequent surgery.
Related education on E/M modifiers, clinical coding practice cases, and documentation audits helps coders distinguish unrelated procedures from separately reportable unrelated visits.
The four-question modifier decision method
Before selecting a modifier, answer these questions in order.
Question 1: Is the second procedure occurring within an applicable postoperative global period?
Verify the original procedure date, the global indicator, the date of the subsequent procedure, and whether the same-physician rules apply.
Question 2: Is the second procedure clinically related to the original surgery?
An unrelated new condition supports consideration of modifier 79. A related condition requires further evaluation.
Question 3: Was the related procedure planned, more extensive, or therapeutic after a diagnostic procedure?
If the documentation establishes a qualifying staged or related circumstance, evaluate modifier 58.
Question 4: Did an unplanned related procedure require a return to an operating or qualifying procedure room?
When the requirements are satisfied, modifier 78 is generally appropriate.
If the second service represents routine postoperative care, is inadequately documented, or falls outside the modifier requirements, further analysis is necessary.
Use medical coding audit checklists, physician query templates, and denial root-cause analysis when the documentation leaves the correct choice uncertain.
Modifier 58 vs 78 vs 79: 32 Surgical Scenarios and Coding Decisions
| Clinical Scenario | Modifier | Reason for Selection | Documentation Required |
|---|---|---|---|
| 1. Planned second-stage flap division following initial reconstruction | 58 | Prospectively planned second stage | Original surgical plan and second operative report |
| 2. Planned complex closure after initial malignant lesion excision | 58 | Staged reconstruction during the global period | Original plan identifying delayed closure |
| 3. Definitive therapeutic excision after diagnostic surgical biopsy | 58 | Therapy follows a diagnostic procedure | Pathology, treatment indication, and operative findings |
| 4. Second-stage tendon reconstruction planned during first operation | 58 | Documented staged treatment strategy | First operative report describing planned stages |
| 5. Planned hardware removal as part of staged orthopedic treatment | 58 | Second stage of a documented surgical plan | Operative plan, timing, and treatment rationale |
| 6. Planned skin graft following initial wound-bed preparation | 58 | Staged definitive reconstruction | Initial operative plan and graft procedure details |
| 7. More extensive resection after an initial limited surgical procedure | 58 | Qualifying more extensive subsequent procedure | Clinical reason for increased extent and operative findings |
| 8. Planned second-stage reconstructive flap transfer | 58 | Anticipated continuation of reconstructive treatment | Documented staged reconstruction plan |
| 9. Serial operative debridement specifically planned as staged treatment | 58 | Planned therapeutic surgical sequence | Prospective plan distinguishing staging from complication treatment |
| 10. Definitive surgery following an initial diagnostic laparoscopic procedure | 58 | Therapy after diagnostic surgery | Diagnostic findings and indication for definitive treatment |
| 11. Postoperative hemorrhage requiring surgical re-exploration | 78 | Unplanned related return to the operating room | Bleeding complication and return operative report |
| 12. Symptomatic postoperative hematoma evacuated in the OR | 78 | Related postoperative complication requiring OR return | Hematoma findings and procedure-room evidence |
| 13. Wound dehiscence requiring operative repair | 78 | Unplanned related return for surgical management | Wound findings and operative repair documentation |
| 14. Deep postoperative infection requiring operative washout | 78 | Related complication treated in the operating room | Infection findings, operative location, and procedure performed |
| 15. Postoperative bowel obstruction related to the first surgery requiring reoperation | 78 | Related unplanned return to the OR | Relationship to initial surgery and reoperation report |
| 16. Anastomotic leak requiring operative repair | 78 | Related postoperative condition requiring OR return | Leak confirmation and operative treatment details |
| 17. Unplanned related endoscopic intervention performed in a qualifying endoscopy suite | 78 | Related procedure in a qualifying procedural setting | Indication, suite location, and procedure report |
| 18. Unplanned nerve decompression related to the original surgical site | 78 | Related return to the operating room | New findings, relationship, and OR documentation |
| 19. Superficial postoperative wound assessment in the office | No 78 | Office evaluation alone does not establish an OR return | Assessment, treatment, and whether care is included in the global package |
| 20. Hand fracture surgery unrelated to an earlier knee operation | 79 | Separate injury and unrelated surgical treatment | Distinct diagnosis, injury history, and operative report |
| 21. Independent carpal tunnel release during recovery from unrelated foot surgery | 79 | Different condition unrelated to the original surgery | Separate medical necessity and procedure details |
| 22. Excision of a new unrelated skin malignancy at another site | 79 | Separate lesion and independent treatment indication | Distinct lesion history, site, and pathology |
| 23. Excision of an unrelated symptomatic cyst during recovery from orthopedic surgery | 79 | Separate condition requiring a distinct procedure | Independent diagnosis and procedure documentation |
| 24. New traumatic injury requiring surgery during an existing global period | 79 | Independent injury unrelated to the original operation | New injury date, evaluation, and operative findings |
| 25. Separately indicated elective surgery for an unrelated condition | 79 | Independent treatment unrelated to the original procedure | Separate medical necessity and surgical indication |
| 26. Second-eye cataract surgery for an independent contralateral condition | 79 | Unrelated surgical treatment during the first eye's global period | Eye-specific diagnosis, laterality, and operative documentation |
| 27. Surgical treatment of an unrelated infection in another extremity | 79 | Distinct disease process with independent treatment | Clinical evidence establishing separate pathology |
| 28. Unrelated hernia repair during recovery from another operation | 79 | Separate diagnosis and surgical indication | Distinct operative reports and medical necessity |
| 29. Routine postoperative suture removal | No 58/78/79 | Usually included in postoperative care | Original global-period rules and service details |
| 30. Bedside management of a postoperative complication without OR return | Generally no 78 | Global complication care is generally included without an OR return | Clinical treatment, procedure setting, and separate-payment exceptions |
| 31. Unrelated office E/M visit during the surgical global period | 24 for eligible E/M | Modifier 24 addresses an unrelated postoperative E/M service | Separate reason for visit and E/M documentation |
| 32. New surgery performed after the original global period has ended | No global modifier solely for timing | The earlier postoperative restriction has expired | Original procedure date, global indicator, and new service date |
Cases are illustrative coding scenarios, with modifier choices conditioned on the documented facts. Confirm the actual CPT/HCPCS code, global indicator, same-physician rules, NCCI edits, and payer requirements before submitting a claim. The examples are educational and do not represent real patient records.
2. Real Surgical Cases: How to Choose Modifier 58, 78, or 79
Case 1: Delayed reconstruction after malignant lesion excision — Modifier 58
A surgeon excises a malignant skin lesion and documents that definitive wound closure will be performed in a separate operative session. The delayed reconstruction is intentionally scheduled while the patient remains within the original postoperative period.
The initial claim describes the lesion excision. The subsequent claim reports the appropriate reconstruction procedure with modifier 58 when all coding requirements are satisfied.
A documented example used in Medicare contractor guidance involves excision code 11606 followed by planned complex repair code 13101 with modifier 58. The actual code selection depends on the current descriptors, anatomical details, and completed procedures.
Why modifier 58 applies: The delayed closure is part of a prospectively planned treatment sequence.
The strongest evidence is the first operative report describing the anticipated second stage. Coders should verify the plan using operative documentation audits, CPT coding guidance, and coding practice scenarios.
Case 2: Diagnostic surgical biopsy followed by definitive treatment — Modifier 58
A patient undergoes a surgical biopsy to establish the nature of a suspicious lesion. Pathology subsequently confirms a condition requiring more extensive therapeutic surgery.
The same surgeon performs the definitive procedure during the postoperative period associated with the original diagnostic operation.
Why modifier 58 applies: The second procedure provides treatment following the diagnostic surgical procedure.
The initial operation must genuinely have been diagnostic, and the later procedure must represent qualifying therapy. The fact that pathology results become available after surgery should be supported by the actual record.
A coder should review the pathology report, initial operative findings, subsequent surgical indication, and correct CPT descriptions. This is particularly important in complex outpatient cases, medical necessity review, and clinical documentation auditing.
Case 3: Postoperative hemorrhage requiring surgical exploration — Modifier 78
A patient undergoes abdominal surgery with a 90-day global period. Four days later, the patient develops significant postoperative bleeding.
The surgeon returns the patient to the operating room, identifies the bleeding source, and performs the necessary surgical treatment.
Why modifier 78 applies: The return was unplanned, the procedure was related to the original operation, and treatment required the operating room.
The subsequent claim reports the procedure actually performed, with modifier 78 when appropriate. It should accurately reflect the reoperation rather than automatically repeating the code for the original surgery.
For Medicare, payment generally reflects the applicable intraoperative portion, and the original global period continues.
Accurate processing requires coding audit controls, claim adjustment analysis, and denial monitoring.
Case 4: Postoperative wound infection treated in the office — Review the global package
A patient returns eight days after surgery with a superficial wound infection. The surgeon examines the incision, prescribes treatment, and provides local wound care in the office.
The visit involves a postoperative complication, but the documented services do not establish a qualifying return to an operating or procedure room.
Coding decision: Evaluate whether the services are included in the original global package. Modifier 78 does not apply solely because a complication occurred.
For Medicare, the global package generally includes the surgeon's treatment of complications that do not require an additional trip to the operating room, subject to applicable exclusions and separate-payment rules.
This is a frequent source of mistaken billing when teams equate every complication with a separately billable service.
Review the encounter using coding audit checklists, medical necessity documentation, and denial root-cause analysis.
Case 5: New hand fracture during recovery from knee surgery — Modifier 79
A patient undergoes knee surgery with a 90-day postoperative global period. Three weeks later, the patient sustains a traumatic hand fracture in an unrelated accident.
The same surgeon, assuming appropriate expertise and payer requirements, subsequently performs surgical treatment of the fracture.
Why modifier 79 applies: The hand injury represents an independent clinical condition unrelated to the knee operation.
The documentation should establish the new injury, the separate medical necessity, and the operative service performed.
Modifier 79 allows the unrelated surgical procedure to be evaluated under its own global surgery rules. A new postoperative period begins for that subsequent operation.
For effective claim preparation, teams should link accurate procedure coding, clinical evidence validation, clean claim monitoring, and coding interview scenarios.
Case 6: Contralateral cataract surgery during the first eye's global period — Modifier 79
A surgeon performs right-eye cataract surgery. Several weeks later, during the first procedure's 90-day postoperative period, the surgeon performs cataract surgery on the left eye for a separately documented cataract.
The second eye has its own diagnosis, surgical indication, and operative record.
Why modifier 79 may apply: The second operation treats an unrelated, separately indicated condition in the other eye.
The distinction should be supported by the actual treatment circumstances, rather than laterality alone. Payer-specific ophthalmology rules and the current surgical code requirements must also be verified.
Coders should preserve laterality and establish the separate condition through coding accuracy review, outpatient procedure exercises, and claim denial analysis.
Case 7: Planned second-stage tendon reconstruction — Modifier 58
A surgeon performs the first stage of tendon reconstruction and explains in the operative documentation that a second operation will be required after the tissue has reached the appropriate healing stage.
The second planned procedure occurs during the original global period.
Why modifier 58 applies: The operative record establishes the staged treatment strategy before the second surgery occurs.
The first operation's documented plan provides stronger support than a retrospective statement added only after the claim is questioned.
This makes operative report review, physician query compliance, and procedure coding education essential to correct billing.
3. How Modifiers 58, 78, and 79 Affect Payment and Global Periods
Modifier 58: A new global period begins
Under Medicare's global surgery rules, modifier 58 identifies a qualifying staged or related subsequent procedure that starts a new postoperative period.
The subsequent operation is generally considered for payment according to its own applicable fee schedule and surgical billing rules. Other adjustments, including multiple-procedure policies or contractual provisions, may still affect reimbursement.
Suppose the original procedure has a 90-day global period. A planned second-stage operation occurs on postoperative day 20 and carries its own 90-day global period.
The second procedure establishes a new postoperative period associated with that operation. Coding and billing teams must track each procedure's relevant global dates accurately because the patient may have overlapping periods of postoperative care.
This is especially important when organizations use automated claim edits or electronic claims platforms.
To reduce payment errors, connect global surgery coding review, CPT code validation, physician fee schedule research, and claim acceptance monitoring.
Modifier 78: Intraoperative payment without restarting the global period
Modifier 78 has a different reimbursement consequence.
For a related return to the operating room, Medicare generally calculates payment using the intraoperative portion of the fee schedule amount for the subsequent procedure when the code has applicable global-package component percentages.
Consider a hypothetical return procedure with an unadjusted Medicare fee schedule amount of $2,400 and an applicable intraoperative percentage of 65%.
The illustrative Medicare payment calculation is:
$2,400 × 0.65 = $1,560
Actual reimbursement depends on the procedure's published payment data and other applicable billing rules. Procedures with a 000 global indicator have different treatment because they do not have a preoperative, intraoperative, and postoperative percentage breakdown.
The original global period continues after a modifier 78 reoperation.
For example, if a patient undergoes surgery on March 1 with a 90-day global period and returns to the operating room on March 12 for a related complication, the March 12 procedure does not restart the original 90-day postoperative period.
Billing teams should verify the fee schedule and the exact procedure performed before calculating reimbursement.
For payment investigation, use Medicare fee schedule guidance, claim adjustment reason code references, denial management resources, and billing appeal templates.
Modifier 79: Independent reimbursement and a separate global period
A qualifying unrelated surgery receives consideration under its own payment and global-period rules when modifier 79 is correctly reported.
Suppose a patient undergoes surgery on January 10 with a 90-day global period. On February 15, the patient requires another operation for an independent condition, and that second procedure also carries a 90-day global period.
Modifier 79 indicates the unrelated nature of the February procedure.
The second operation establishes its own postoperative period while the first procedure's global period continues according to its original dates.
The two global periods can overlap. This matters when coders subsequently evaluate office visits, surgical complications, or additional procedures.
A later encounter could be related to the first operation, the second operation, both, or an entirely different condition. The documented clinical relationship determines the appropriate billing treatment.
This requires strong coding audit controls, medical necessity verification, E/M modifier knowledge, and denial prevention procedures.
The overlooked same-physician rule
Medicare generally treats physicians in the same group practice and the same specialty as a single physician for global surgery purposes.
If one surgeon performs the original operation and another surgeon from the same specialty and group performs the subsequent procedure, the global surgery requirements still need to be evaluated.
A different physician name on the second claim does not automatically remove global-period restrictions.
Organizations should verify group relationships, provider specialty information, and the applicable payer rules when reviewing these cases.
This is particularly relevant for multisurgeon practices, shared postoperative care, and professional fee coding.
Accurate provider mapping supports clean claim rates, coding audit accuracy, and reimbursement validation.
Quick Poll: What Causes the Most Global Surgery Modifier Errors in Your Practice?
4. Documentation Requirements That Support Modifiers 58, 78, and 79
A correct modifier choice requires documentation that explains the circumstances of the subsequent procedure. Audit teams should be able to reconstruct the reasoning from the medical record without relying on assumptions about the surgeon's intention.
Documentation checklist for modifier 58
The operative documentation should establish the staged or related treatment circumstances.
For a planned second stage, the initial record should ideally identify the anticipated procedure or describe the treatment strategy that requires subsequent intervention.
For a more extensive procedure, the record should explain the clinical findings and treatment circumstances supporting the increased extent.
For therapy following diagnostic surgery, the documentation should establish the initial diagnostic purpose and the subsequent therapeutic indication.
The record should also support the second procedure's medical necessity and the actual service performed.
A retrospective amendment created solely to justify payment creates audit concerns. Any correction or clarification must accurately reflect the clinical facts and follow appropriate documentation policies.
Coders can strengthen these reviews using medical coding audit checklists, compliant provider query examples, CPT coding resources, and medical coding practice cases.
Documentation checklist for modifier 78
Modifier 78 requires evidence of an unplanned related return to a qualifying operating or procedure room.
The return procedure's operative report should identify the clinical indication, relevant postoperative findings, treatment performed, and procedural setting.
For example, an operative report describing evacuation of a postoperative hematoma should make the relationship to the earlier procedure apparent.
The medical record should also establish that the subsequent encounter involved a return to the appropriate procedural environment.
A patient receiving wound treatment at the bedside presents a different billing circumstance from a patient taken to the operating room for surgical exploration.
When documentation simply states that the patient underwent postoperative wound care, the coding team needs more information before determining whether the service meets modifier 78 requirements.
Use physician query templates, coding compliance checklists, and denial investigation procedures to resolve questionable cases.
Documentation checklist for modifier 79
Modifier 79 requires a documented distinction between the original surgical treatment and the subsequent operation.
The new diagnosis, separate medical necessity, and second operative report should support the conclusion that the procedure is unrelated.
A different diagnosis code can strengthen the documentation, but the code alone may be insufficient to establish the actual clinical relationship.
For example, a patient undergoing another operation at the original surgical site may still have a genuinely unrelated condition. Conversely, a procedure on a separate anatomical structure may remain connected to the original operation.
Reviewers should evaluate the complete treatment history.
This approach helps protect medical coding accuracy, medical necessity compliance, claim acceptance rates, and revenue cycle performance.
Global surgery edits involving modifiers 24, 25, and 57
Surgical claims often involve both procedure modifiers and E/M modifiers. Applying the correct modifier to the correct code is essential.
Modifier 24 identifies an unrelated E/M service performed during a postoperative period when applicable requirements are met. It is appended to the E/M code.
Modifier 25 identifies a significant, separately identifiable E/M service on the same date as a procedure or another service. The documentation must support work above and beyond the usual associated care.
Modifier 57 identifies an E/M service that resulted in the initial decision to perform major surgery, generally involving a 90-day global period under Medicare rules.
Modifiers 58, 78, and 79 identify qualifying subsequent procedures during a global period. They should be evaluated in relation to the surgery itself.
For example, when a postoperative patient presents with an unrelated condition requiring a separate office evaluation, modifier 24 may be relevant. If the patient also undergoes an unrelated operation, modifier 79 may apply to the qualifying procedure code. Each reported service requires its own support.
Coders should review modifier 24 versus 25 versus 57 guidance, modifier 25 versus 59 examples, coding practice cases, and compliance audit methods.
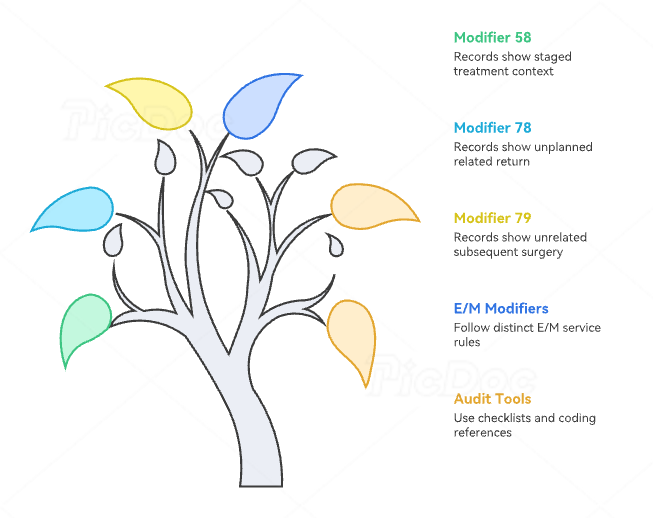
5. Common Modifier 58, 78, and 79 Denials and How to Prevent Them
Mistake 1: Reporting modifier 58 for an unexpected postoperative complication
One common error is selecting modifier 58 because a subsequent operation is related to the first surgery.
A patient may require more extensive treatment after complications arise, but the circumstances still require careful evaluation. Modifier 58 supports qualifying staged, more extensive, or therapeutic procedures. An unplanned related return to the operating room to address a postoperative problem generally calls for modifier 78.
The coder should examine why the subsequent operation occurred and whether it was part of the original treatment strategy.
Corrective action: Compare the operative reports, original treatment plan, and reason for the return. Use coding audit procedures, CPT coding references, and compliant physician clarification when documentation is unclear.
Mistake 2: Using modifier 78 without a qualifying return to the operating room
A patient develops a minor postoperative wound problem and receives treatment during an office visit. The billing team appends modifier 78 because the service relates to the original surgery.
The claim may be denied because the documented circumstances fail to establish the required return to an operating or procedure room.
Corrective action: Verify the procedure setting and whether the service is already included in postoperative care. Analyze related denials through claim adjustment reason codes, denial rate worksheets, and coding audit checklists.
Mistake 3: Assuming that different anatomical sites automatically justify modifier 79
Separate anatomical locations can provide evidence of unrelated treatment, but the underlying clinical circumstances remain important.
For example, additional procedures involving another structure may be part of a planned staged reconstruction or treatment of the original condition.
The coding decision should reflect the relationship between the conditions and procedures.
Corrective action: Compare diagnoses, surgical indications, anatomical sites, and the original operative plan. Strengthen the review through medical necessity documentation, outpatient coding scenarios, and clinical documentation audits.
Mistake 4: Restarting the global period after modifier 78
An incorrect billing-system configuration may start a new postoperative period whenever a second surgical claim is processed.
This creates inaccurate global dates for patients who undergo an unplanned related return to the operating room.
Under Medicare rules, modifier 78 does not restart the original postoperative period. Qualifying modifier 58 and modifier 79 procedures begin new postoperative periods.
Corrective action: Configure the practice management system to distinguish the three modifiers, validate procedure-specific global indicators, and test the results using fictional patient timelines.
Link this review with physician fee schedule resources, electronic claims software, clean claim rate monitoring, and coding compliance audits.
Mistake 5: Adding another modifier simply to bypass a global surgery denial
When a postoperative claim is denied as bundled, billing teams may be tempted to append another modifier to obtain payment.
Modifier 59, for example, addresses distinct procedural services under applicable circumstances and coding edits. It does not replace the clinical requirements governing modifiers 58, 78, or 79.
A more defensible response begins with determining the actual reason for the denial.
Corrective action: Examine the original surgical claim, global-period dates, second operative report, modifier assignment, and payer explanation.
If the denial is incorrect, prepare an appeal with supporting evidence. Relevant resources include modifier 25 versus 59 guidance, medical billing appeal templates, denial management services, and claim adjustment reason code references.
Build a global surgery modifier audit that catches errors before submission
A practical audit should examine the original procedure, global indicator, subsequent procedure date, provider relationship, clinical circumstances, modifier assignment, and expected payment treatment.
Start by sampling claims containing modifiers 58, 78, and 79. Include denied claims and claims that were paid without apparent problems, since payment alone does not establish accurate coding.
Record each error according to its root cause: incorrect relationship determination, missing operative evidence, improper global-period calculation, wrong procedure code, or payer policy misunderstanding.
Then measure the error rate for each modifier separately.
For example, if a practice reviews 100 modifier 78 claims and identifies 12 unsupported assignments, its audited error rate is 12% for that sample. Investigating those 12 claims can reveal whether the main issue involves documentation, coder training, or system configuration.
Use findings to update coding audit checklists, denial root-cause worksheets, coder productivity reviews, and claim accuracy monitoring.
Repeat the audit after training and compare results by procedure type, coder, surgeon, and payer. This helps demonstrate whether corrective action is reducing actual coding risk.
6. FAQs About Modifiers 58, 78, and 79
-
Modifier 58 identifies a qualifying staged or related procedure during the postoperative period, including procedures planned in advance, more extensive procedures, or therapeutic procedures following diagnostic surgery.
Modifier 78 applies to an unplanned related return to a qualifying operating or procedure room.
Modifier 79 identifies an unrelated procedure performed during an existing postoperative global period.
Correct selection depends on the clinical relationship, original treatment plan, and second procedure's circumstances. Coders should practice these distinctions using outpatient coding cases, CPT coding resources, and coding audit guidance.
-
Modifiers 58 and 79 begin new postoperative periods for their qualifying subsequent procedures under Medicare rules.
Modifier 78 generally preserves the original global period without restarting it.
When several surgeries occur during overlapping global periods, coding teams should maintain separate timelines for the relevant operations.
Accurate tracking supports clean claim calculations, medical billing compliance, and physician reimbursement analysis.
-
Modifier 58 can be appropriate for a qualifying more extensive procedure or therapy following diagnostic surgery, even when every detail of the subsequent treatment was unknown at the original encounter.
An unplanned return to the operating room for treatment of a related postoperative problem generally falls under modifier 78.
The clinical circumstances determine the choice.
Coders should examine the first and second operative reports, review the reason for additional treatment, and use compliant physician queries when clarification is appropriate.
-
The return must occur in a qualifying operating or procedure room under the relevant rules.
Medicare recognizes certain specifically equipped and staffed procedural environments, including endoscopy suites, cardiac catheterization suites, and laser suites.
Routine bedside care, a minor treatment room, or an ordinary postoperative office examination does not automatically satisfy the requirement.
Documentation should establish where the procedure occurred and what treatment was performed.
Teams should incorporate these checks into coding audit procedures, medical necessity reviews, and denial investigation workflows.
-
Yes, when the second procedure treats a condition genuinely unrelated to the original surgery and the remaining modifier requirements are satisfied.
For example, a surgeon may perform an unrelated hand procedure during the global period of an earlier foot operation.
The record should establish the separate diagnosis, surgical indication, and medical necessity. Anatomical differences alone may leave important questions unanswered.
For practice, review realistic outpatient coding scenarios, coding interview questions, and coding compliance checklists.
-
These modifiers are used to identify qualifying surgical or procedural services during a postoperative period.
For eligible E/M services, other modifiers may apply depending on the circumstances.
Modifier 24 addresses unrelated E/M services during a postoperative period. Modifier 25 addresses significant, separately identifiable E/M services on the same day as another procedure or service. Modifier 57 addresses an E/M service resulting in the initial decision for major surgery.
Coders should review modifier 24 versus 25 versus 57 guidance, modifier 25 versus 59 examples, and coding audit standards.
