
A radiologist interprets a CT scan, the imaging center performs it, and both submit claims. One incorrect modifier can trigger duplicate billing, lost reimbursement, or a payer audit. Modifier 26 identifies the professional component; modifier TC identifies the technical component. However, their correct use depends on Medicare's PC/TC indicator, service ownership, documentation, and place of service. This guide explains the billing decisions behind each modifier, with practical examples for CPT coding, coding audits, denial prevention, and physician reimbursement.
1. Modifier 26 vs TC: What Each Modifier Means and When to Use It
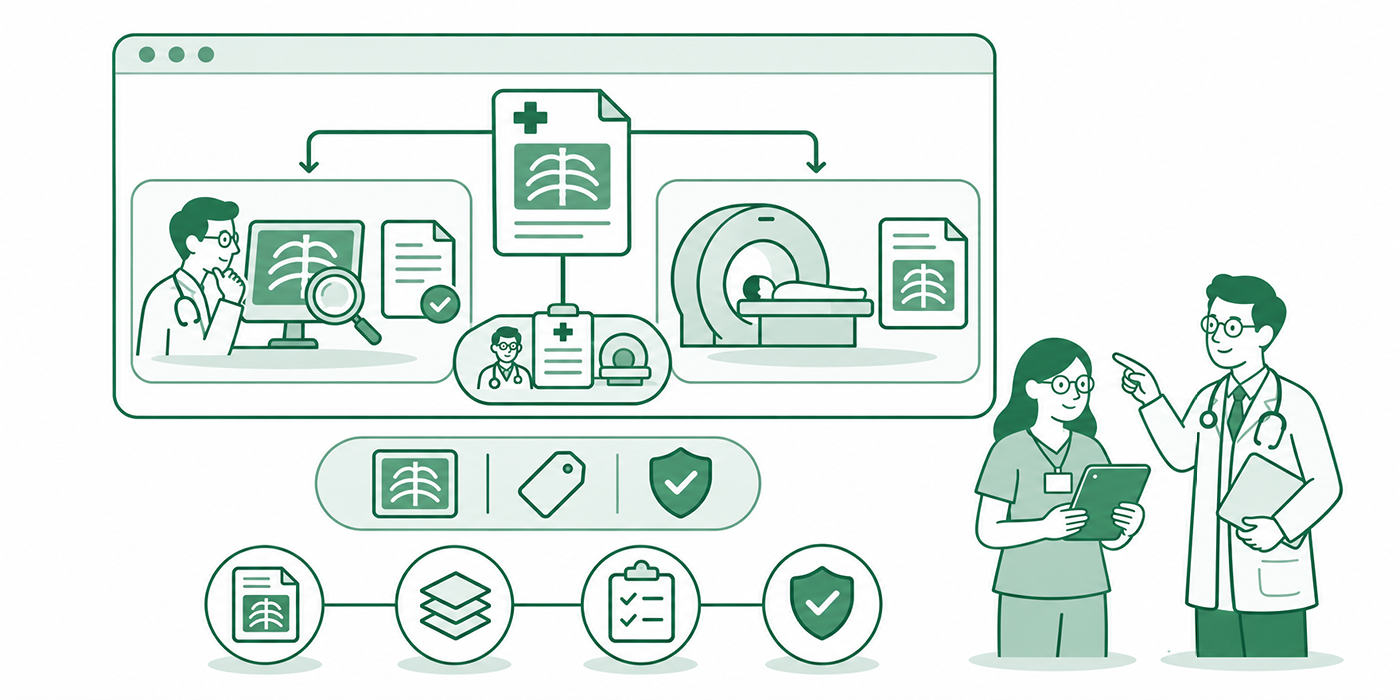
Certain diagnostic procedures contain two separately identifiable components. The professional component covers clinical interpretation and associated professional work. The technical component covers the resources necessary to produce the diagnostic study.
A radiology group interpreting an MRI performed at a hospital may bill the professional component, while the hospital accounts for the technical portion through its applicable facility billing methodology.
Understanding the distinction is essential when reviewing medical coding accuracy, electronic claims submissions, physician fee schedules, and claim adjustment reason codes.
Modifier 26: Professional Component
Modifier 26 reports the professional portion of an eligible diagnostic service.
This typically includes interpreting diagnostic findings, producing the required written report, and the associated professional work. The professional component also carries applicable practice expense and malpractice expense relative value units.
Example: A hospital performs a two-view chest X-ray (71046). An independent radiologist interprets the images and prepares the required report.
Radiologist: 71046-26
Hospital: Reports its technical services through the applicable facility claim process.
The radiologist must have performed a billable interpretation. Merely reviewing an existing report, acknowledging the findings, or documenting an incidental opinion does not automatically support another professional interpretation charge.
This distinction becomes critical in coding compliance audits, documentation clarification, medical necessity reviews, and denial investigations.
Modifier TC: Technical Component
Modifier TC reports the technical portion of an eligible diagnostic service.
It covers qualifying equipment, supplies, technical personnel, and other resources used to acquire the study. The entity furnishing the technical component must satisfy applicable supervision, enrollment, coverage, and billing requirements.
Example: A freestanding imaging center performs a CT scan of the head without contrast (70450), but an independent radiologist provides the interpretation.
Imaging center: 70450-TC
Interpreting radiologist: 70450-26
This split is appropriate when both components qualify for separate reporting and the respective billing entities are eligible to submit them.
For small-practice billing systems, electronic claim platforms, Medicare billing operations, and revenue leakage analysis, correctly identifying which entity furnished the technical component prevents duplicate or unsupported charges.
Global Billing: When Neither Modifier Is Needed
A global diagnostic claim represents both the professional and technical portions of an eligible procedure.
For example, a properly enrolled independent imaging practice performs a chest X-ray using its equipment and obtains the professional interpretation through its own appropriately structured operation.
When all global-billing requirements are satisfied, it may report 71046 without modifier 26 or TC.
Global reporting also requires attention to Medicare payment locality rules, ownership and purchased-service arrangements, and the specific payer's billing policies.
A practice should verify these conditions before switching a claim from separately reported components to global reporting. Otherwise, the change may create issues in reimbursement calculations, claim denial analysis, coding quality assurance, and medical billing appeal workflows.
Modifier 26 vs TC: 35 Coding Scenarios and Billing Decisions
| Procedure or Situation | Correct Reporting | Reason | Critical Billing Check |
|---|---|---|---|
| 1. Chest X-ray interpreted by outside radiologist | 71046-26 | Professional interpretation only | Verify the written radiology report |
| 2. Chest X-ray performed at freestanding imaging center | 71046-TC | Technical acquisition only | Confirm ownership, supervision, and technical billing eligibility |
| 3. Entire chest X-ray service furnished by eligible practice | 71046 | Complete global service | Confirm both components and global billing conditions |
| 4. CT head interpreted remotely | 70450-26 | Interpretation of noncontrast head CT | Verify interpreting provider and location |
| 5. CT head performed by independent imaging center | 70450-TC | Scanner and technical acquisition resources | Confirm technical component was furnished |
| 6. Entire head CT performed and interpreted by eligible entity | 70450 | Professional plus technical components | Check global eligibility and geographic payment rules |
| 7. Chest CT with contrast interpreted by radiologist | 71260-26 | Professional interpretation | Verify study type, contrast use, and report |
| 8. Chest CT with contrast performed at freestanding center | 71260-TC | Qualifying technical portion | Validate acquisition and separate supply reporting rules |
| 9. Lumbar MRI interpreted externally | 72148-26 | Professional MRI interpretation | Confirm final report and interpreting provider |
| 10. Lumbar MRI performed by independent imaging center | 72148-TC | Equipment and technical acquisition | Verify site and technical responsibility |
| 11. Complete abdominal ultrasound interpreted externally | 76700-26 | Professional ultrasound interpretation | Confirm complete study documentation |
| 12. Complete abdominal ultrasound technically furnished | 76700-TC | Technical component of the ultrasound | Verify acquisition and staff requirements |
| 13. Echocardiogram interpreted by outside cardiologist | 93306-26 | Professional echocardiography interpretation | Ensure the reported examination matches the study |
| 14. Echocardiogram technically performed by eligible center | 93306-TC | Ultrasound acquisition and technical resources | Confirm technical documentation |
| 15. Carotid duplex interpreted by specialist | 93880-26 | Professional vascular study interpretation | Verify complete bilateral study and findings |
| 16. Carotid duplex performed by diagnostic center | 93880-TC | Technical vascular imaging component | Verify appropriate study acquisition |
| 17. Sleep study interpreted by independent physician | 95811-26 | Professional interpretation | Confirm complete study and physician report |
| 18. Sleep study conducted by eligible sleep center | 95811-TC | Technical sleep-study component | Verify technical service and supervision standards |
| 19. Surgical pathology specimen interpreted externally | 88305-26 | Pathologist's professional work | Confirm specimen interpretation and report |
| 20. Surgical pathology specimen processed by eligible laboratory | 88305-TC | Technical pathology processing | Check setting-specific restrictions |
| 21. Surgical pathology with both components furnished globally | 88305 | Complete eligible pathology service | Validate who furnished both components |
| 22. Higher-complexity surgical pathology interpreted externally | 88307-26 | Professional pathology interpretation | Verify appropriate specimen-level code |
| 23. Higher-complexity pathology technically processed | 88307-TC | Technical pathology work | Confirm laboratory and patient-setting rules |
| 24. Complete 12-lead ECG service | 93000 | Dedicated global ECG code | Do not append 26 or TC |
| 25. ECG tracing without interpretation | 93005 | Dedicated tracing-only code | Do not append TC |
| 26. ECG interpretation and report only | 93010 | Dedicated interpretation-only code | Do not append 26 |
| 27. Complete cardiovascular stress test | 93015 | Dedicated complete-service code | Verify required service elements |
| 28. Cardiovascular stress test supervision only | 93016 | Dedicated supervision component | Do not append 26 automatically |
| 29. Cardiovascular stress test tracing only | 93017 | Dedicated tracing component | Do not append TC |
| 30. Cardiovascular stress test interpretation only | 93018 | Dedicated interpretation component | Do not append 26 |
| 31. Established-patient office E/M | 99213 | Ordinary E/M service | Neither 26 nor TC applies |
| 32. Routine automated blood count | 85025 | Clinical laboratory testing | Do not treat routine lab work as a split diagnostic service |
| 33. Hospital X-ray technically furnished by hospital | Facility claim; physician 71046-26 | Institutional technical billing and physician interpretation | Avoid separate physician-office technical claims |
| 34. Eligible global imaging test interpreted in another MPFS locality | Separate component claims | Global billing locality requirements may prevent one claim | Verify service and interpretation addresses |
| 35. Physician reviews another physician's existing report | No automatic second PC claim | Routine report review does not establish a separately billable interpretation | Check for a distinct covered service and documentation |
Examples illustrate component decisions under typical Medicare rules. Confirm current-year PC/TC indicators, CPT descriptors, payer policies, provider eligibility, and place-of-service rules before submitting claims. Hospital facility reporting may use institutional billing conventions rather than modifier TC.
2. How to Check Medicare PC/TC Indicators Before Adding Modifier 26 or TC
The Medicare Physician Fee Schedule Database assigns a professional component/technical component indicator to procedure codes. This indicator determines whether a code supports component billing under Medicare.
A common source of preventable denials is applying modifier 26 or TC simply because a service involved a physician and equipment. The actual code may already describe a professional-only service, a technical-only service, or a complete service with separate component codes.
Before submitting a claim, verify the code's current indicator using the appropriate Medicare billing resources, review the applicable physician fee schedule, confirm CPT code selection, and apply the relevant coding audit controls.
Understand the Nine Medicare PC/TC Indicator Categories
Indicator 0: Physician service codes. The professional/technical component concept does not apply. Common E/M services fall into this category. Adding modifier 26 to an ordinary office visit creates an invalid component designation.
Indicator 1: Diagnostic tests with separately identifiable components. These codes generally support modifier 26, modifier TC, or global reporting when the associated requirements are satisfied. This is the principal category for separately billed radiology, diagnostic testing, and certain pathology services.
Indicator 2: Professional-component-only codes. The code itself already identifies the professional service. CPT 93010, representing ECG interpretation and report, is an example. Adding modifier 26 would duplicate the professional-component designation.
Indicator 3: Technical-component-only codes. The code already identifies the technical service. CPT 93005, representing ECG tracing without interpretation and report, is an example. Modifier TC is unnecessary.
Indicator 4: Global-test-only codes. These codes identify complete services for which separate professional and technical component codes exist. Modifiers 26 and TC are not appropriate for the global-only code.
Indicator 5: Incident-to codes. Separate PC/TC modifier reporting does not apply. Billing depends on the underlying coverage and incident-to requirements.
Indicator 6: Laboratory physician interpretation codes. These identify certain separately payable physician interpretation services. Modifier TC is inappropriate; any modifier 26 use requires checking the specific code and Medicare's applicable interpretation rules.
Indicator 7: Private-practice therapist services. This indicator relates to specialized Medicare payment restrictions for therapist services rather than routine professional/technical splitting.
Indicator 8: Physician interpretation of certain clinical laboratory tests. This includes the specific Medicare treatment of code 85060, with payment restrictions tied to qualifying abnormal-smear interpretations for hospital inpatients.
Indicator 9: PC/TC concept does not apply. There is no applicable professional-versus-technical split for the code.
These categories should be included in coder training and claim-edit configuration. They are particularly valuable when developing coding practice assessments, medical coding interview tests, medical coding audit checklists, and claim denial analysis worksheets.
The Five-Question Modifier Eligibility Test
For every potential professional/technical split, answer these questions before releasing the claim:
Does the code support component billing? Verify the current PC/TC indicator and any code-specific exceptions.
Who furnished the technical service? Identify the organization responsible for the equipment, technical staff, acquisition, and supervision.
Who performed the professional interpretation? Verify the interpreting clinician, professional responsibility, and required report.
Where were the components furnished? Confirm the actual service locations, facility status, and Medicare payment locality.
Who has the right to bill each component? Validate enrollment, contractual arrangements, payer requirements, and purchased-service restrictions.
Consider an imaging practice that owns the scanner but sends studies to a radiologist working in another Medicare payment locality. Both components may have been arranged by the same organization, yet Medicare's locality rules can require separate reporting rather than a global claim.
The decision must be supported by actual service information rather than a billing-system default. Incorrect defaults can produce avoidable denials, distort clean claim calculations, delay accounts receivable collections, and complicate medical necessity appeals.
3. Modifier 26 vs TC Coding Examples for Radiology, Cardiology, and Pathology
The most effective way to learn component billing is to identify what happened clinically, determine who furnished each part, and select the corresponding claim structure.
The following examples use established coding patterns. Always verify current-year descriptors, component indicators, and payer rules through CPT coding references, Medicare reimbursement guidance, coding audit procedures, and claim submission resources.
Example 1: CT Scan Performed at a Hospital, Interpreted by a Radiologist
A hospital performs a noncontrast head CT, code 70450. An independently billing radiologist interprets the examination and creates the required report.
Correct reporting:
Radiologist professional claim: 70450-26
Hospital: Technical services reported through the applicable institutional billing methodology.
Why this matters: A professional group that submits global 70450 would be attempting to report technical resources furnished by the hospital. Conversely, an imaging center that reports 70450-TC must establish that it furnished the technical portion and is eligible to bill it.
Investigate incorrect component reporting through medical coding audits, claim adjustment code reviews, Medicare billing references, and denial root-cause worksheets.
Example 2: Echocardiogram at a Freestanding Cardiology Center
A freestanding diagnostic center performs a complete echocardiographic examination qualifying for code 93306. A separate cardiologist interprets the images and produces the report.
Correct reporting:
Center: 93306-TC
Cardiologist: 93306-26
If one eligible billing entity furnishes both components under the applicable requirements, global code 93306 may be appropriate.
The coder should also confirm that the documented study supports the complete examination represented by 93306. Correct modifier selection cannot compensate for choosing an unsupported procedure code.
For this reason, component reviews should include outpatient coding case validation, documentation query procedures, medical necessity criteria, and coding accuracy checks.
Example 3: ECG Performed in an Office With a Separate Interpretation
An office records a 12-lead ECG. Another physician performs the interpretation and prepares the report.
Correct reporting:
Office furnishing the tracing: 93005
Interpreting physician: 93010
The component-specific codes already exist. Appending TC to 93005 or modifier 26 to 93010 is inappropriate under Medicare's coding structure.
If the same eligible practice furnishes the complete ECG service, 93000 may apply instead.
This case illustrates why code-family selection should occur before modifier selection. The same principle is tested in medical coding employment assessments, outpatient coding exercises, coding certification preparation, and routine coding compliance reviews.
Example 4: Surgical Pathology Specimen Processed by a Laboratory and Interpreted Elsewhere
A qualifying surgical pathology specimen is processed by an eligible independent laboratory, and a pathologist working for a separate organization performs the professional interpretation.
Assuming CPT 88305 accurately represents the specimen and payer rules permit separate reporting:
Technical provider: 88305-TC
Interpreting pathologist: 88305-26
Pathology component claims require particular attention to patient setting. Medicare restricts certain independent laboratory technical-component billing for services furnished to hospital inpatients or outpatients.
The laboratory's possession of the specimen does not independently establish a right to bill the technical component.
Verify the patient setting, actual laboratory work, applicable payment restrictions, and relationship between billing entities. These details are essential for coding audit documentation, claim reimbursement analysis, denial investigation, and appeal documentation preparation.
Example 5: Cardiovascular Stress Testing With Separate Service Codes
A cardiovascular stress test may involve distinct supervision, tracing, and interpretation services.
The relevant code family includes:
93015: Complete qualifying stress test service.
93016: Supervision-only service.
93017: Tracing-only service.
93018: Interpretation and report only.
The correct code depends on which elements were furnished. Appending 26 or TC to these already component-specific codes is inappropriate.
This is particularly important when automated billing systems attempt to use modifier TC for every technical diagnostic test. The correct approach is to select the appropriate code family before applying component logic.
Compare such decisions against CPT examination resources, coding practice questions, claim editing workflows, and denial prevention controls.
Quick Poll: What Is Your Biggest Modifier 26 vs TC Billing Problem?
Your selection displays targeted guidance on this page. Responses are not collected or stored.
4. Modifier 26 and TC Billing Rules for Hospitals, Imaging Centers, and Physician Offices
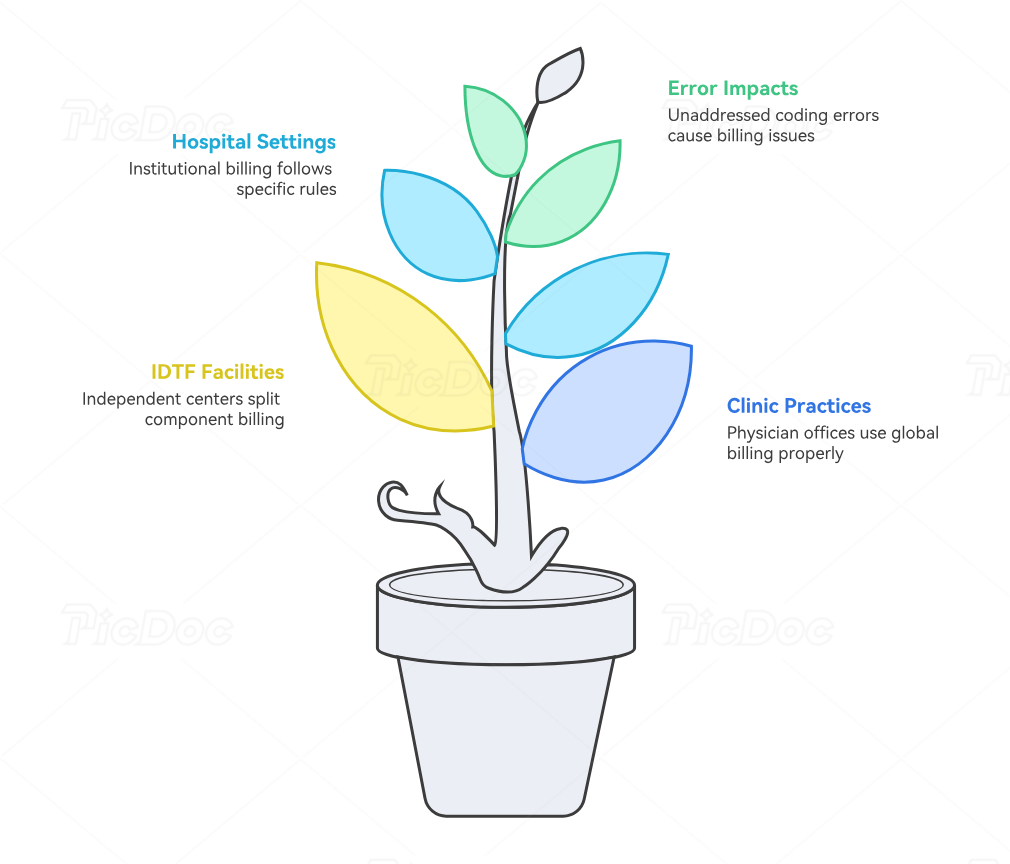
The same diagnostic procedure can require different claim structures depending on the treatment setting and which organization furnished the service.
A coder who selects modifiers based entirely on the CPT code can miss ownership restrictions, billing-location requirements, and institutional payment arrangements. These errors frequently surface through duplicate claim denials, reimbursement audits, claim adjustment reason codes, and delayed accounts receivable.
Hospital Inpatient and Outpatient Settings
When a hospital furnishes the technical component of an imaging service, the hospital typically accounts for that service through its institutional billing arrangements.
An independently billing radiologist providing the professional interpretation generally reports the eligible diagnostic code with modifier 26.
The hospital's institutional claim may use a different reporting format from an independent physician's professional claim. Therefore, the absence of modifier TC from a hospital facility claim does not automatically establish a billing error.
Practical audit scenario: A radiology group bills 72148 globally for an MRI performed using hospital-owned equipment. If the group furnished only the interpretation, the global claim is inappropriate. The correct professional reporting would generally be 72148-26, assuming the interpretation and all other billing conditions are supported.
The technical portion remains subject to the hospital's applicable payment rules.
For audit teams, compare the billed component against the actual service location, hospital ownership records, and interpretation documentation. This should be incorporated into medical coding audit checklists, Medicare billing reviews, denial analysis procedures, and medical necessity investigations.
Independent Diagnostic Testing Facilities and Freestanding Imaging Centers
An independent diagnostic testing facility (IDTF) or eligible freestanding imaging center may furnish the technical component of certain diagnostic tests.
If a separate radiology practice interprets those studies, each entity generally reports the component it furnished, subject to Medicare enrollment, supervision, and purchased-service requirements.
Three operational checks are particularly valuable:
Confirm that the location and billing entity meet the requirements for the technical component.
Confirm the professional interpretation was furnished by a qualified clinician and documented in an identifiable report.
Determine whether the parties' arrangements permit separate billing or qualifying global billing, including applicable anti-markup restrictions.
Purchased diagnostic tests and purchased interpretations can create additional Medicare payment limitations. A practice should review those rules before treating a subcontracted interpretation as though it were performed by its own employed physician.
This becomes especially important when selecting medical billing software, configuring electronic claims platforms, calculating physician reimbursement, and evaluating coding compliance risks.
Physician Offices and Multispecialty Group Practices
A physician-owned office may properly report a global diagnostic service when the entity furnishes both components and satisfies the relevant billing requirements.
Consider a cardiology group with its own echocardiography equipment, technical personnel, and interpreting cardiologists. When the group's arrangements satisfy the applicable rules, reporting the complete eligible service may be appropriate.
If the group performs the technical portion and an independent physician separately bills the interpretation, the claims may instead be divided into TC and 26 components.
The practice's billing system should capture the actual interpreting clinician, technical location, billing entity, and relationship between the components.
A useful control is to reconcile completed studies against both technical acquisition records and professional reports before claim release. This helps protect clean claim performance, strengthen coding accuracy, reduce insurance denials, and improve revenue cycle tracking.
5. Modifier 26 vs TC Reimbursement, Denials, and Audit Prevention
Professional and technical components have different reimbursement values because they represent different resources.
Under Medicare's PC/TC indicator 1 structure, the professional component's relative value units include physician work, practice expense, and malpractice expense. The technical component's relative value units reflect practice and malpractice expenses associated with performing the technical service.
The global relative value units generally equal the sum of the two component relative value units. Actual payment depends on applicable fee schedules, geographic adjustments, contractual arrangements, and payment policies.
These distinctions matter when comparing physician fee schedule reimbursement, Medicare billing requirements, claim adjustment codes, and accounts receivable performance.
Example: Calculate the Financial Impact of Incorrect Component Billing
Suppose a hypothetical payer contract establishes the following amounts for a diagnostic service in a particular setting:
Global allowable amount: $400
Professional component allowable amount: $140
Technical component allowable amount: $260
If the radiologist furnished only the professional interpretation, the applicable component allowance would be $140 under these assumed terms.
Submitting the global code would improperly seek reimbursement for the technical service that the radiologist did not furnish.
If the claim were paid globally at $400, the difference between that amount and the hypothetical professional allowance would be $260, subject to validation of the actual payment and contractual rules.
For a batch of 100 similarly affected claims, the potential discrepancy would be $26,000 before considering payer adjustments, reversals, or other applicable factors.
This example is illustrative; professional and technical allowances are code-specific and should never be assigned a universal percentage split.
To establish actual financial exposure, reconcile payments using reimbursement references, claim denial root-cause analysis, coding audit documentation, and appropriate billing appeal procedures.
The Six Most Important PC/TC Denial Patterns
1. Invalid modifier for the procedure code. Modifier 26 or TC is attached to a code that does not permit the requested component. The correction begins with verifying the PC/TC indicator and selecting the proper code.
2. Global billing when only one component was furnished. The claim includes an unsupported portion of the service. Review acquisition records, interpretation reports, and billing eligibility before submitting a corrected claim.
3. Duplicate professional interpretation claims. More than one professional claim appears for a single study without separately supported and payable work. Investigate the clinical reports, provider assignments, and claim history.
4. Incorrect technical-component ownership. A physician group bills technical services that were actually furnished by a hospital or another entity. Verify the responsible provider and patient setting.
5. Missing or insufficient interpretation documentation. The physician submits modifier 26 without the documentation needed to establish a separately billable interpretation.
6. Geographic or purchased-service billing conflicts. The claim structure fails to reflect the location or contractual arrangement governing diagnostic component payment.
Each denial type requires a different corrective action. Grouping all six under a general modifier-error category prevents teams from finding the underlying cause.
A department should link these errors to denial-rate calculations, clean claim rate monitoring, medical coding audit findings, and reimbursement recovery workflows.
Build a Pre-Bill Component Validation Workflow
A high-performing diagnostic billing process should verify the following information before claims leave the system:
Procedure eligibility: Current code, applicable PC/TC indicator, valid code status, and payer rules.
Service attribution: Performing organization, technical resources, interpreting physician, and any purchased-service arrangement.
Documentation: Completed technical acquisition records and a separately identifiable professional interpretation when applicable.
Claim structure: Appropriate global, professional-only, technical-only, or dedicated component code.
Location and payment: Actual place of service, relevant Medicare payment locality, claim format, and contractual requirements.
Duplicate prevention: Review existing professional, technical, and global claims for the same diagnostic service.
After implementation, measure whether invalid-component denials decline and whether corrected claims are receiving appropriate payment. Incorporate those results into coding productivity evaluations, medical coding accuracy audits, revenue cycle performance reporting, and payer denial management.
6. Frequently Asked Questions About Modifier 26 vs TC
-
Modifier 26 identifies the professional component of an eligible diagnostic service, generally involving physician interpretation and the required report. Modifier TC identifies the technical component, including qualifying equipment, personnel, and acquisition resources.
Both modifiers require an eligible procedure code and appropriate billing circumstances. Check Medicare's current PC/TC indicator before selecting either modifier.
For additional review, use CPT coding resources, physician reimbursement guidance, medical coding audit procedures, and coding practice cases.
-
A single claim line generally should not carry both modifiers to represent one complete diagnostic service. When one eligible billing entity furnishes both components, the applicable global procedure code is ordinarily reported without either modifier.
When different eligible entities furnish the components, separate professional and technical claims may be appropriate.
Review the component reporting rules in your Medicare billing workflow, verify the applicable fee schedule rules, and check for duplicate claim denials.
-
A separately billed diagnostic interpretation generally requires documentation of a qualifying professional interpretation, including the required written report.
The documentation should establish the physician's professional work and distinguish it from routine review of another clinician's findings.
A physician reviewing an imaging report during a separate office visit does not automatically qualify to bill another professional imaging interpretation.
This is a critical issue in documentation compliance audits, physician query reviews, medical necessity assessments, and coding error investigations.
-
Hospitals commonly account for their technical imaging services through institutional billing arrangements. These claims may follow facility-specific reporting conventions and may not require an explicit TC modifier.
An independently billing physician interpreting the study generally reports the professional component using modifier 26 when the procedure permits component billing.
The appropriate process depends on the payer, claim type, and patient setting. Consult Medicare billing resources, electronic claims submission guidance, coding audit checklists, and claim adjustment references.
-
CPT 93010 already represents ECG interpretation and report. It is a stand-alone professional-component code under Medicare's payment-indicator system.
Adding modifier 26 would attempt to apply a component modifier to a code that already defines that component.
Similarly, 93005 identifies the tracing-only portion and does not require modifier TC.
These distinctions should be reinforced through CPT exam practice questions, outpatient coding cases, and coding accuracy reviews.
-
Certain pathology and diagnostic laboratory-related services permit a professional-component distinction. Surgical pathology code 88305, for example, supports component reporting when the applicable conditions are met.
However, routine clinical laboratory tests generally do not qualify for modifier 26 merely because a physician reviews the results.
Medicare also has specific payment rules for laboratory physician interpretations and certain abnormal-smear interpretations. Verify the exact service and payment indicator before billing.
This area requires particular care during coding audits, medical coding training, physician reimbursement reviews, and claim denial investigations.
