
Medical Billing Appeal Letter Templates for 15 Common Claim Denials
A denial letter becomes useful only when it attacks the payer's specific adjudication reason with evidence. Generic requests to “please reconsider” waste appeal windows and create avoidable rework. Teams that understand claim adjustment reason codes, maintain disciplined denial-management workflows, submit through reliable electronic claims platforms, and understand core medical billing concepts can turn appeals into targeted reimbursement arguments. The 15 templates below are built around that principle.
1. Diagnose the Denial Before Writing the Appeal Letter
The most expensive appeal mistake happens before anyone writes a sentence: the billing team assumes every unpaid claim requires an appeal.
Some claims need a corrected claim. Others need medical records, eligibility correction, coordination-of-benefits information, a reconsideration request, contractual underpayment review, or a formal appeal. Strong revenue-cycle teams separate these pathways immediately instead of feeding every denial into the same queue.
Start with the ERA or EOB. Under HIPAA administrative-simplification rules, health plans use standardized Claim Adjustment Reason Codes (CARCs) and Remittance Advice Remark Codes (RARCs) to explain payment adjustments. CMS continues updating those code sets and related Medicare remittance systems in 2026. Your first task should therefore be identifying the complete denial message rather than working from a shortened description in a practice-management system.
The AMBCI CARC reference directory, a structured insurance denial-management process, accurate electronic claim submission, and strong medical billing knowledge should work together here. A CARC tells you why the payment changed; the accompanying RARC can narrow the problem substantially.
Before appealing, answer six questions:
What exactly did the payer deny? Identify the claim, individual line, units, date of service, procedure, and dollar amount.
What rule did the payer apply? Find the plan policy, contract provision, NCCI edit, benefit limitation, authorization rule, medical policy, or filing requirement behind the decision.
Was the original claim actually correct? A coding mistake belongs in a corrected-claim workflow more often than an appeal. Teams familiar with CPT coding principles, professional versus facility coding, coding audit methodology, and coding interview-style case analysis should validate coding before blaming adjudication.
What fact overturns the denial? Your appeal needs a decisive fact: qualifying documentation, authorization confirmation, proof of timely submission, separate procedural circumstances, eligibility history, primary-payer EOB, or coverage-policy criteria.
What evidence proves that fact? Never make the reviewer hunt through 70 pages of records for the argument.
What deadline and submission route apply? Commercial plans, Medicare Advantage, Medicaid, workers' compensation, and Original Medicare can use different appeal pathways. Teams dealing with Medicaid billing, workers' compensation billing, physician reimbursement, or ambulance reimbursement should maintain payer-specific calendars rather than one generic deadline.
For Original Medicare fee-for-service, a first-level redetermination generally must be requested within 120 days after receipt of the initial determination. A dissatisfied party can then request QIC reconsideration, generally within 180 days after receipt of the redetermination. CMS specifically instructs appellants to identify the disputed services, explain why they disagree, and submit relevant evidence.
That is the standard your internal appeal letters should imitate even when another payer uses different forms: identify, explain, prove, request.
| Denial Scenario | Best First Route | Evidence to Pull | Critical Question Before Sending |
|---|---|---|---|
| 1. Medical necessity denial | Appeal | Clinical note, policy criteria, diagnostics | Which documented facts satisfy coverage criteria? |
| 2. No prior authorization | Appeal only if exception/error exists | Authorization logs, emergency facts, payer calls | Was authorization required and obtainable? |
| 3. Authorization number missing | Correct/reprocess | Authorization confirmation | Was authorization valid on the service date? |
| 4. Authorized units exceeded | Appeal disputed units | Authorization, treatment records, unit history | Were additional units clinically and contractually allowable? |
| 5. Timely filing denial | Exception request or payer-specific dispute | Clearinghouse acceptance, claim-control history | Can receipt within the filing period be proven? |
| 6. Duplicate claim | Reprocessing inquiry first | Original claim status, replacement indicator | Was this truly a duplicate or a corrected/distinct claim? |
| 7. Modifier missing | Corrected claim when original coding was wrong | Procedure note, modifier criteria | Did documentation support the modifier on DOS? |
| 8. Modifier rejected | Appeal if original coding was correct | Documentation, NCCI/payer policy | What documented circumstance supports separation? |
| 9. Bundled service | Validate edit before appeal | Current NCCI edit, operative note | Does the edit permit separate reporting? |
| 10. MUE/unit denial | Appeal when medically reasonable units are documented | Units, dosage, treatment note | Do records explain every disputed unit? |
| 11. Diagnosis/procedure mismatch | Coding review first | Diagnosis documentation, coding guidelines | Was diagnosis coding accurate on the original claim? |
| 12. Invalid diagnosis | Corrected claim | Date-specific ICD code set | Was the code valid for the date of service? |
| 13. Place-of-service mismatch | Correct or appeal depending on original accuracy | Location records, claim form | Where was the service actually rendered? |
| 14. Provider-type mismatch | Enrollment/coding review | Credentialing and enrollment records | Was the rendering provider eligible for this service? |
| 15. NPI/taxonomy mismatch | Correct/reprocess | Enrollment confirmation | Does payer enrollment match claim data? |
| 16. Patient ineligible | Eligibility dispute if payer data is wrong | Eligibility response, enrollment history | Was coverage active on the exact DOS? |
| 17. COB information missing | Update COB/reprocess | Primary EOB, COB confirmation | Which payer was primary on DOS? |
| 18. Wrong primary payer | Bill correct payer first | Coverage chronology | Has payer order been established? |
| 19. Non-covered benefit | Appeal only when benefit interpretation is wrong | Benefit booklet, plan policy | Is the service genuinely excluded? |
| 20. Experimental/investigational | Clinical appeal | Medical policy, evidence, patient-specific rationale | Which policy criterion is disputed? |
| 21. Frequency limitation | Appeal if exception or payer error exists | Prior service history, medical necessity | Why was additional frequency necessary? |
| 22. Records not received | Resubmit documentation | Transmission confirmation | Can prior record delivery be proven? |
| 23. Records insufficient | Appeal with indexed evidence | Complete relevant medical record | What specific missing element caused denial? |
| 24. Invalid patient demographics | Corrected claim | Member card, registration data | Does claim data exactly match payer records? |
| 25. Contractual underpayment | Payment dispute | Contract, fee schedule, EOB | What should the allowed amount have been? |
| 26. Multiple-procedure reduction dispute | Payment-policy review | Fee schedule, reduction methodology | Was the reduction correctly applied? |
| 27. Secondary payer rejects balance | COB review | Primary EOB, crossover data | Did secondary receive complete primary adjudication? |
| 28. Ambulance medical-necessity denial | Clinical appeal | PCS where applicable, transport record, origin/destination | Why was another means of transport unsafe? |
| 29. Medicaid rate/payment dispute | State-specific payment review | Rate methodology, claim detail | Was the correct state rate and methodology applied? |
| 30. Workers' compensation denial | Jurisdiction-specific dispute | Authorization, causation, fee schedule | Which workers' compensation rule controls the bill? |
2. Use These 15 Medical Billing Appeal Letter Templates for Common Denials
These templates are intentionally short. A powerful appeal letter should make the reviewer understand the dispute within seconds, then direct the reviewer to the evidence. Teams using billing software for smaller practices, managing electronic claim submission, researching denial-management services, or interpreting CARCs and adjustment messages should save payer-specific versions rather than sending identical language everywhere.
Each template assumes you first confirmed that an appeal is the correct route.
Template 1: Medical Necessity Denial
Re: Claim [number], DOS [date], member [ID], CPT/HCPCS [code]
We request reconsideration of the denial for [service] based on medical necessity. The enclosed record documents [patient condition/severity], including [specific symptoms, examination findings, diagnostic results, failed conservative treatment, risk factors, or clinical deterioration]. These findings satisfy the applicable coverage criteria because [briefly map facts to payer policy].
Please overturn the denial and reprocess the claim for payment. Relevant supporting documentation is indexed as follows: [policy], [progress note], [diagnostic results], and [treatment history].
A successful medical-necessity appeal connects documentation directly to the payer's rule. A long chart dump is weaker than a short argument tied to objective evidence. This is especially important in physician reimbursement disputes, ambulance reimbursement, coding-audit work, and medical billing careers.
Template 2: Prior Authorization Was Obtained but Claim Denied
Authorization [number] was approved for [service/code], [units], provider [name], and dates [range]. The service rendered on [DOS] falls within that approved scope. The enclosed authorization confirmation verifies the approval, and the claim information matches the authorized service.
We request that the authorization denial be reversed and claim [number] reprocessed according to the member's benefits and provider contract.
Attach the authorization itself rather than a staff note saying authorization existed. Compare code, units, servicing provider, site, date range, and member ID. Strong claims-submission controls, denial workflows, billing software, and billing-concept training should capture these fields before service delivery.
Template 3: No Prior Authorization but an Exception Applies
We request reconsideration of the authorization denial for [service]. Prior authorization could not reasonably be obtained because [emergency circumstances / payer eligibility information / retroactive coverage / payer-directed exception]. The attached documentation establishes [specific facts].
Because the circumstances meet [payer policy or contractual exception], we request retrospective review of medical necessity and payment of the claim.
Avoid inventing an exception after the denial. The appeal must identify a real contractual, regulatory, emergency, or payer-policy pathway. Teams handling Medicaid billing, workers' compensation billing, ambulance claims, and commercial denial management should keep separate authorization-exception rules.
Template 4: Timely Filing Denial
Claim [number] was submitted on [date], within the payer's filing requirement of [period]. Attached evidence includes [clearinghouse acceptance report / payer claim-control acknowledgment / electronic submission report], showing receipt or successful transmission on [date].
We request reversal of the timely-filing denial and reprocessing based on this documented submission history.
For Medicare, be especially careful. Medicare generally requires claims within 12 months of the date of service, and CMS states that a denial based solely on untimely filing does not constitute an initial determination subject to ordinary appeal. CMS recognizes defined exceptions, including certain administrative errors, retroactive entitlement, and retroactive disenrollment situations.
That makes proof-of-filing discipline essential in electronic claims systems, small-practice billing platforms, denial management, and revenue-cycle billing work.
Template 5: Modifier Denial
We request reconsideration of the denial involving modifier [modifier]. The modifier was reported because [specific documented circumstance]. The enclosed documentation identifies [separate E/M work / distinct anatomic site / separate encounter / repeat procedure / other qualifying circumstance] and supports separate reporting under the applicable coding and payer rules.
Please reprocess the affected line based on the documented services.
Never add a modifier simply because a claim denied. Validate the original code combination first. Coders applying CPT coding rules, developing professional-fee coding skills, preparing for coding interview tests, or progressing toward coding auditing should document the exact fact supporting the modifier.
Template 6: Bundling or NCCI Denial
Claim line [code] was denied as bundled into [code]. The services were separately reportable because [separate site / separate encounter / qualifying clinical circumstance]. The attached operative/procedure record documents [specific evidence].
The applicable edit permits separate reporting when an appropriate modifier is supported. We therefore request reversal and reprocessing of the denied line.
CMS's Medicare NCCI PTP edits identify code pairs ordinarily inappropriate to report together; the Column Two code may be payable when the edit permits an associated modifier and the clinical circumstances genuinely support it. CMS updates these files quarterly.
This is where coding audit expertise, CPT knowledge, denial management, and claim-adjustment analysis protect revenue without turning modifiers into automatic edit bypasses.
Template 7: Duplicate Claim Denial
Claim [number] was denied as a duplicate of claim [prior number]. The denied submission represents [a corrected claim / distinct service / separate encounter / previously unprocessed line] rather than a duplicate billing of the same service.
The attached claim history and documentation distinguish the two submissions. Please review the claim relationship and reprocess the current claim accordingly.
Check claim frequency codes, replacement indicators, original payer control numbers, dates, units, and line-level adjudication before appealing. Duplicate denials often originate in electronic claim workflows, practice billing software, denial queues, or rushed work under billing and coding productivity pressure.
Template 8: Eligibility Denial Despite Active Coverage
The claim was denied for inactive eligibility; however, attached eligibility records show that member [ID] had active coverage on [DOS]. The verification response dated [date] confirms coverage effective [date range].
Please update the eligibility determination for the service date and reprocess claim [number].
Do not rely solely on a screenshot that lacks member identity or service-date applicability. Eligibility evidence should be traceable. This is particularly important in Medicaid billing systems, small-practice billing workflows, electronic claims submission, and broader medical billing operations.
Template 9: Coordination of Benefits Denial
Claim [number] was denied because coordination-of-benefits information was incomplete or incorrect. [Payer name] was [primary/secondary] on the date of service. Attached documentation includes the primary payer EOB and current coverage information establishing the correct payer order.
Please update the COB record and reprocess this claim using the enclosed primary adjudication information.
COB appeals fail when teams send only the secondary claim again. Include the primary EOB and explain payer order. The process should be integrated into electronic claims workflows, billing-software configuration, denial-management operations, and medical billing training.
Template 10: Non-Covered Service Denial
We request reconsideration of the non-covered-service denial for [service]. The member's applicable benefit documents and payer policy indicate coverage when [criterion]. The enclosed records demonstrate [facts satisfying criterion].
Please review the cited benefit provision and supporting clinical documentation and reprocess the claim.
First determine whether the service is truly excluded from the benefit package. Medical necessity cannot create a benefit where the contract expressly excludes one. Teams comparing Medicaid reimbursement, physician fee schedules, workers' compensation billing rules, and commercial denial services must separate coverage from payment amount.
Template 11: Frequency-Limit Denial
The payer denied [service] because the stated frequency limit was exceeded. Additional service on [DOS] was medically necessary because [change in condition, recurrence, high-risk status, failed prior intervention, or other documented circumstance].
The enclosed records document the clinical exception and prior service history. We request review under the payer's exception process and payment for the disputed service.
A strong frequency appeal establishes both the prior utilization history and the reason another service was needed. That combination matters for teams interpreting medical necessity, analyzing CARC denials, managing appeal workloads, and improving coding accuracy under productivity pressure.
Template 12: Place-of-Service Denial
We request reconsideration of the place-of-service denial for claim [number]. The service was rendered at [location/type of setting], and POS [code] accurately reflects that setting. The attached encounter and facility records confirm the location on [DOS].
Please review the supporting documentation and reprocess the claim using the originally submitted place of service.
When the original POS was wrong, file the appropriate corrected claim instead. Payment rules can change materially by setting, making physician fee-schedule knowledge, professional-versus-facility coding, coding auditing, and claims submission particularly relevant.
Template 13: Diagnosis-to-Procedure Inconsistency Denial
Claim [number] was denied because the diagnosis was considered inconsistent with procedure [code]. The reported diagnosis [code] accurately reflects the condition documented on [DOS]. The enclosed note demonstrates [relevant symptoms, diagnosis, findings, or treatment indication] supporting the relationship between the diagnosis and service.
Please reconsider the denial based on the submitted clinical documentation and applicable coverage criteria.
Validate diagnosis coding before appealing. A coding error should be corrected rather than defended. Professionals building medical terminology knowledge, CPT expertise, coding interview readiness, and auditing careers should distinguish documentation support from coding correction.
Template 14: Records Missing or Insufficient
We request reconsideration of the denial stating that documentation was missing or insufficient. Enclosed are the records specifically supporting [medical necessity / procedure performed / units / diagnosis / authorization criterion], including [list documents].
For ease of review, the relevant evidence appears on pages [X–Y], where [briefly state decisive fact]. Please reconsider the denial using the complete attached record.
CMS review contractors use defined denial/non-affirmation reasons when medical-review documentation fails to establish Medicare requirements. An indexed evidence packet makes the appeal materially stronger than blindly retransmitting the chart. That discipline belongs in denial management, coding audits, electronic claim systems, and billing operations.
Template 15: Contractual Underpayment or Incorrect Allowed Amount
Payment for claim [number] does not match the contracted reimbursement methodology. Under [contract section / fee schedule / amendment], the expected allowed amount for [code/service] is [amount or formula]. The payer allowed [amount].
Attached are the applicable contractual provision, claim detail, and remittance. We request adjustment of the allowed amount and payment of the resulting balance.
This dispute is strongest when it shows the mathematics. Compare contracted rate, multiple-procedure rules, units, locality, modifiers, patient responsibility, and prior payer payment. The AMBCI physician reimbursement guide, Medicaid rate calculator, ambulance reimbursement guide, and workers' compensation resources can help teams isolate the applicable payment methodology.
3. Build an Appeal Packet That Makes the Reviewer’s Job Easy
A persuasive appeal packet should allow a reviewer to answer three questions quickly: What was denied? Why was the payer's conclusion wrong? Where is the proof?
Start with a one-page appeal letter. Put member name, member ID, claim number, date of service, provider, disputed code, billed amount, denial reason, and requested outcome near the top. Teams using electronic claim platforms, billing solutions, denial-management services, or CARC references should auto-populate these fields wherever possible.
The argument itself should have four pieces:
Denial: “The payer denied CPT 12345 for medical necessity.”
Disagreement: “The denial applied criterion X, while the patient met criterion Y.”
Evidence: “The MRI dated X and note dated Y document the required findings.”
Requested action: “Reverse the denial and reprocess the claim.”
Then index attachments. A clinical appeal might include the denial notice, original claim, authorization, physician note, diagnostic testing, prior-treatment history, payer medical policy, and a focused physician statement. A coding dispute may need the operative note, current coding guidance, relevant payer edit, and evidence supporting the modifier. These skills overlap heavily with coding-auditor work, professional-fee coding, CPT expertise, and medical billing knowledge.
Avoid three weak habits.
First, do not send irrelevant documentation merely to create volume. Reviewers need decisive evidence.
Second, do not quote a policy without connecting it to the patient's facts. “The service was medically necessary” is a conclusion. “Policy requires A, B, and C; pages 4, 7, and 9 document A, B, and C” is an argument.
Third, do not miss the procedural requirements of the appeal itself. For Medicare QIC reconsideration, CMS asks for specific service and date information, identification of the contractor, an explanation of disagreement, and supporting evidence; CMS also advises submitting relevant evidence at that stage because later introduction can require showing good cause.
This evidence discipline becomes especially important where billing stress, productivity quotas, outsourced revenue-cycle work, and complex coding specialties create pressure to close accounts quickly.
4. Escalate Denials With a Payer-Specific Appeal Strategy
An appeal template should standardize structure while the substance remains payer-specific.
Original Medicare fee-for-service uses a formal multi-level appeals structure beginning with MAC redetermination and moving to QIC reconsideration. CMS requires first-level redetermination requests generally within 120 days after receipt of the initial determination; second-level reconsideration is generally requested within 180 days after receipt of the redetermination. Commercial plans and Medicare Advantage plans can use different contractual and regulatory timelines, so the denial notice itself should be treated as an operational document.
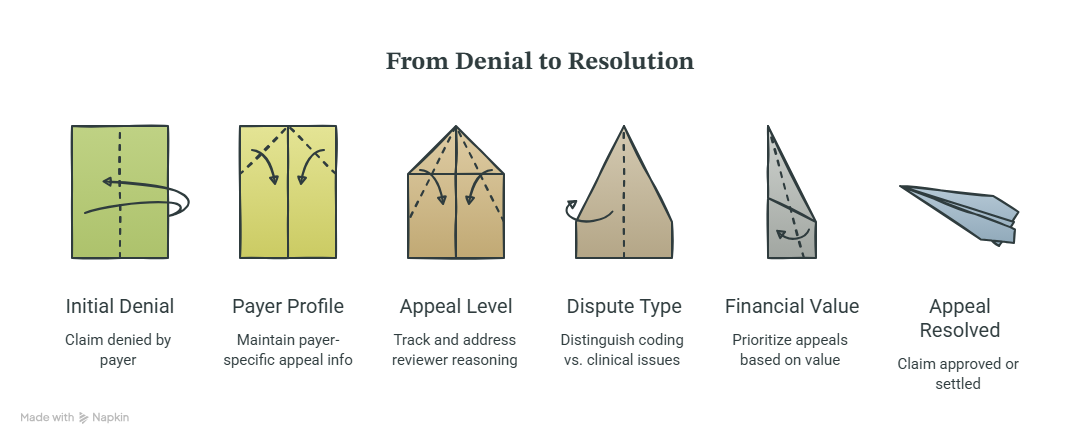
For every payer, maintain a profile containing appeal deadline, reconsideration deadline, portal or mailing destination, fax rules, required form, attachment size limits, provider-dispute route, clinical peer-review route, escalation contact, and whether corrected claims must precede appeals. That profile should sit beside your electronic claims directory, denial-management resources, CARC library, and practice billing software.
Track the appeal level too. Repeating the same letter at level two adds little value. A second-level appeal should address the first reviewer's reasoning directly:
“Redetermination stated X. The record on page 6 documents Y. Policy section Z requires Y. Therefore, the stated basis for denial does not match the submitted evidence.”
That structure turns escalation into targeted rebuttal.
Also distinguish coding disputes from clinical disputes. A modifier, bundling, or diagnosis issue may need an experienced coder. Medical necessity may benefit from a physician or clinician statement. Contractual underpayment belongs with contract-management staff. COB belongs with billing. Eligibility may require registration or payer enrollment data. This is why organizations need more than generic medical billing skills; sophisticated appeals combine coding expertise, auditing judgment, and denial-management operations.
Finally, track the financial value of escalation. A $12 denial should rarely receive the same manual labor as a $12,000 denial. Score accounts using balance, probability of overturn, days remaining, repeat-denial potential, and precedent value. A small denial affecting hundreds of future claims may deserve immediate attention because fixing its root cause can outperform collecting one large isolated account.
5. Turn Appeal Results Into a Denial-Prevention System
A strong appeals team eventually makes itself less busy.
Every overturned denial contains prevention intelligence. If medical necessity appeals routinely win because the information existed in the chart from the beginning, the organization has a claim-documentation or submission problem. If authorization appeals frequently win because valid authorizations fail to flow onto claims, the organization has a systems-integration problem. If modifier appeals repeatedly succeed, coding or claim-edit logic may need revision.
Track denials by payer, CARC/RARC, CPT/HCPCS, provider, location, denial category, dollar value, overturn rate, appeal level, days to resolution, and root cause. The combination of a CARC directory, reliable claims-submission platforms, capable denial-management services, and appropriate billing software makes this analysis much easier.
Then calculate more useful metrics than “number of appeals sent.”
Track:
Preventable denial rate: How many denied claims originated from registration, coding, authorization, documentation, or submission errors?
Appeal overturn rate by category: A 75% overturn rate on one denial category can indicate poor payer adjudication, poor initial claim presentation, or both.
Net dollars recovered: Measure cash, not merely letters submitted.
Average days from denial to appeal: Delayed work erodes filing windows and cash flow.
Repeat denial rate after corrective action: This tells you whether your “fix” changed anything.
Appeal cost per recovered dollar: A high-cost appeal workflow can destroy the value of small recoveries.
Professionals experiencing medical coding productivity pressure, denial-related job stress, outsourcing pressure, or movement toward higher-level coding specialties become more valuable when they can identify recurring revenue leakage rather than merely work queues faster.
Build prevention rules from actual appeal outcomes. If POS denials rise, audit location mapping. If COB denials rise, strengthen front-end insurance verification. If timely-filing denials rise, monitor clearinghouse rejections daily. If NCCI denials rise, review claim edits and coder education. If Medicaid payments are inconsistent, compare against state reimbursement methodology. If physician allowed amounts look wrong, review the physician fee schedule. If transport claims fail repeatedly, use the ambulance reimbursement guide. If workers' compensation bills stall, isolate the applicable workers' compensation billing requirements.
The financial goal extends beyond winning appeals. The best denial is the one that never enters the appeal queue.
6. FAQs About Medical Billing Appeal Letters
-
Include the patient/member name, member ID, provider information, claim number, date of service, disputed code or service, denial reason, reason for disagreement, requested action, and a concise list of supporting documents. Good teams combine this information with CARC analysis, denial-management procedures, electronic claim records, and billing-system data.
-
Most routine provider appeals can make the core argument in one focused page, with evidence attached separately. Complex medical-necessity, contractual, inpatient, or multi-line disputes may need more explanation. Length should follow complexity. Professionals using coding-audit principles, CPT knowledge, billing concepts, and denial-management systems should prioritize evidence density over page count.
-
No universal appeal workflow fits every denial. Coding errors, demographic mistakes, missing authorization numbers, COB updates, invalid diagnoses, and certain duplicate submissions may require correction or reprocessing instead. The triage process should use the CARC and RARC information, the payer's instructions, claims-submission history, and your denial-management workflow before staff generate a letter.
-
Lead with the exact disputed decision and the decisive reason it should change. For example: “We request reconsideration of the medical-necessity denial because the attached record documents all three coverage criteria specified in policy X.” That approach is stronger than a generic request for review. It mirrors the analytical skills used in coding audits, coding interview tests, professional-fee coding, and denial review.
-
Use objective transmission evidence: clearinghouse acceptance reports, payer acknowledgments, claim-control numbers, portal history, EDI reports, or evidence supporting a recognized filing exception. A practice should retain these records through its electronic claims platform, billing solution, and denial-management process. Medicare's filing rules require particular care because ordinary untimely-filing denials follow rules different from standard claim appeals.
-
Obtain the payer's exact medical policy, identify every applicable criterion, and map each criterion to a page or section of the medical record. Add a clinician statement when the record needs context, while avoiding assertions unsupported by contemporaneous documentation. This method works particularly well for physician reimbursement disputes, ambulance claims, coding audits, and organized insurance denial management.
