
Prior Authorization Checklist + Complete Medical Billing Workflow
Prior authorization failures rarely begin at the payer portal. They begin when eligibility is checked too late, the wrong CPT code is submitted, clinical documentation misses a coverage criterion, or an approval expires before the service occurs. A disciplined authorization workflow protects scheduling, reimbursement, and patient trust simultaneously. This guide connects prior authorization with medical billing fundamentals, electronic claim submission, denial management, and physician reimbursement so every authorization can be followed from insurance verification through final payment.
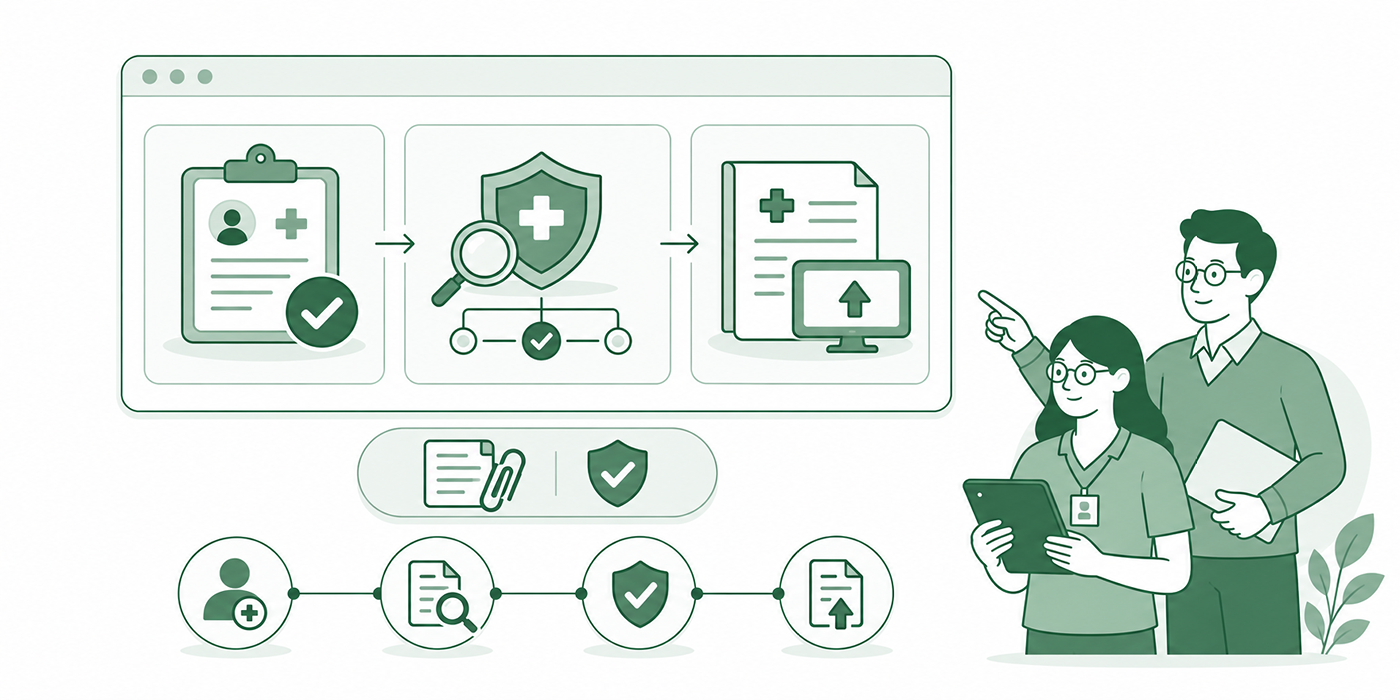
1. Treat Prior Authorization as a Pre-Service Revenue Control, Not a Payer Form
Prior authorization should begin before a service becomes financially committed. Once a costly procedure has been performed, discovering that authorization was required turns a preventable front-end error into a difficult medical billing denial, an avoidable patient-balance dispute, or a write-off.
The first question is therefore not “How do we submit the authorization?” It is “Does this exact patient, plan, procedure, site, provider, and date require authorization?”
That distinction matters because authorization requirements can vary by payer, product, network, CPT or HCPCS code, diagnosis, rendering location, provider participation status, and sometimes treatment frequency. Staff working from an old spreadsheet can create the same kind of avoidable revenue leakage that occurs when outdated physician fee schedule information, incorrect Medicaid reimbursement assumptions, or stale claim adjustment reason-code logic enters the revenue cycle.
Start by confirming the patient's active coverage on the expected date of service. Eligibility checked six weeks earlier may no longer be reliable if the patient changed employers, switched plans, entered a new benefit year, or moved from one Medicaid arrangement to another. A strong billing workflow verifies coverage again close enough to the service date to catch meaningful changes.
Next, identify the exact service. “MRI,” “surgery,” “injection,” or “therapy” is too vague for authorization work. The staff member needs the expected CPT or HCPCS code, diagnosis information, quantity or units where relevant, place of service, ordering provider, rendering provider, and facility. Accurate code identification depends on the same discipline used in CPT coding, professional-fee coding, and outpatient coding.
Then check whether the payer requires authorization, precertification, notification, referral, step therapy, or another utilization-management process. These terms are sometimes treated casually in offices, even though they can trigger different payer requirements. The team handling electronic claims should know exactly what pre-service evidence must exist before a claim reaches billing.
Authorization also needs a clinical owner. Billing staff can identify payer requirements, but they cannot manufacture documentation showing failed conservative treatment, disease severity, imaging findings, medication history, functional limitation, or other medical-necessity criteria. The ordering clinician's documentation must support what is being requested. This is where accurate medical coding, disciplined coding audits, and strong denial prevention overlap.
Most importantly, an authorization approval does not guarantee payment. The eventual claim still has to satisfy eligibility, benefits, coding, documentation, medical necessity, network, modifier, timely-filing, coordination-of-benefits, and payer-processing requirements. An approved procedure submitted with the wrong code can still become a CARC-related adjustment, a coding-related denial, or a reimbursement variance requiring comparison with the applicable fee schedule.
30-Point Prior Authorization Checklist: From Order to Paid Claim
| # | Checkpoint | What to Verify | Failure It Prevents |
|---|---|---|---|
| 1 | Patient identity | Name, DOB, member details match payer record | Eligibility mismatch |
| 2 | Coverage status | Plan is active for expected service date | Inactive-coverage denial |
| 3 | Plan/product | HMO, PPO, MA, Medicaid, commercial, etc. | Wrong payer workflow |
| 4 | Primary/secondary order | Coordination of benefits is current | COB rejection |
| 5 | Network status | Ordering, rendering, and facility participation | Out-of-network nonpayment |
| 6 | Referral requirement | Referral exists when plan requires one | Missing-referral denial |
| 7 | Exact service | Requested procedure is clearly defined | Authorization-service mismatch |
| 8 | CPT/HCPCS | Expected code matches requested service | Wrong-code authorization |
| 9 | Diagnosis | Supported ICD-10-CM diagnosis accompanies request | Medical-necessity failure |
| 10 | Units/quantity | Requested number of units, visits, or treatments | Exhausted authorization |
| 11 | Place of service | Office, ASC, outpatient hospital, etc. | Site mismatch |
| 12 | Ordering provider | NPI and payer requirements are correct | Invalid ordering provider |
| 13 | Rendering provider | Authorized provider matches expected performer | Provider mismatch |
| 14 | Facility | Authorized location matches scheduled location | Facility mismatch |
| 15 | Authorization requirement | Current payer source confirms requirement | Missed authorization |
| 16 | Coverage policy | Applicable medical policy is identified | Unsupported request |
| 17 | Clinical criteria | Chart addresses payer's required criteria | Clinical denial |
| 18 | Conservative treatment | Required prior therapies are documented | Step-therapy/criteria denial |
| 19 | Supporting records | Notes, imaging, labs, therapy history attached | Insufficient-information request |
| 20 | Submission channel | Portal, API, fax, phone, or other accepted method | Unreceived request |
| 21 | Submission proof | Date, confirmation, case number retained | No proof during dispute |
| 22 | Request status | Pending, approved, denied, or more information needed | Forgotten request |
| 23 | Authorization number | Reference entered exactly into billing system | Claim-auth mismatch |
| 24 | Effective date | Authorization begins before service date | Premature service |
| 25 | Expiration date | Service occurs before authorization expires | Expired-auth denial |
| 26 | Approved units | Remaining visits/units checked before each service | Over-utilization denial |
| 27 | Schedule match | Date, provider, facility, and service still match approval | Post-approval mismatch |
| 28 | Claim coding | Billed codes correspond with actual service and approval | Authorized-but-denied claim |
| 29 | Claim outcome | Payment, denial, or request is monitored | Unworked A/R |
| 30 | Root-cause feedback | Authorization-related denials feed process improvement | Repeated front-end failures |
2. Complete the Prior Authorization Request With Documentation That Can Survive Payer Review
Once you confirm authorization is required, build the request from the payer's actual coverage criteria, rather than sending a generic pile of chart notes.
A common failure pattern is technically submitting “documentation” while never answering the payer's decision questions. Twenty pages of records may still fail to establish duration of symptoms, failed conservative treatment, imaging findings, functional impairment, previous medication trials, disease severity, or the reason a lower-intensity treatment is inappropriate.
Start with the payer's current medical policy or authorization requirements. The goal is to understand what evidence changes the decision. This resembles high-quality medical coding work: documentation should drive the result rather than assumptions, medication lists, or loosely related findings.
Match the request to the documentation. If the planned procedure is represented by one CPT code but the authorization was submitted under another, an eventual clean claim may still fail because the payer approved the wrong service. Teams handling CPT coding, professional-fee services, and coding audits should therefore participate when code selection materially affects authorization.
Also verify site of service. A payer may authorize a procedure in an office, ambulatory surgery center, imaging facility, or other setting under different rules. If the patient is later moved to a hospital outpatient department, do not assume the original approval automatically follows. Site changes can affect both authorization and the physician reimbursement structure.
The same discipline applies to provider changes. If the scheduled rendering clinician changes, confirm whether the authorization is tied to a specific NPI, TIN, facility, or network relationship. A valid authorization in one configuration may fail when the actual claim contains another.
Every submission should generate a trackable record: request date, channel, confirmation number, payer case number, requested service, requested units, status, assigned owner, expected response deadline, last follow-up date, and next action. This information belongs in the practice's billing system or another controlled work queue rather than someone's email inbox or handwritten notebook.
For impacted payers under CMS's interoperability and prior-authorization rule, certain medical-item and service authorization decisions must generally be sent within 72 hours for expedited requests and seven calendar days for standard requests beginning in 2026; specific program rules and allowable extensions can affect particular cases. CMS also requires specific denial reasons for impacted requests. These requirements cover specified CMS-regulated payers and should not be generalized to every commercial plan or every drug authorization.
When the payer requests additional information, treat the request like a countdown rather than an ordinary inbox task. Determine exactly what is missing, obtain it from the clinical team, send it through the accepted channel, retain transmission evidence, and confirm that the payer attached it to the case. A document that was faxed is not necessarily a document that was indexed to the authorization.
When approval arrives, validate the approval itself. Compare the authorization number, CPT or HCPCS code, units, dates, rendering provider, facility, and any limitations with the intended service. This verification belongs in the same workflow as electronic claims submission, denial prevention, CARC analysis, and reimbursement review.
3. Connect Prior Authorization to the Complete Medical Billing Workflow
Prior authorization is one control inside a much larger revenue cycle. The safest workflow is a closed loop in which information captured before service follows the claim until payment and any defect feeds back upstream.
Stage 1: Patient Registration and Insurance Capture
Collect demographics, subscriber information, payer details, member IDs, relationship to subscriber, and coordination-of-benefits information accurately. A claim cannot be rescued by perfect CPT coding if the insurance record belongs to the wrong plan or contains an invalid member ID.
Practices selecting billing software for small medical practices should evaluate whether registration information flows reliably into eligibility, authorization, claims, remittance posting, and A/R work queues.
Stage 2: Eligibility, Benefits, Network, Referral, and Authorization Check
Verify active coverage, patient cost sharing, network status, referral requirements, authorization requirements, and relevant benefit limitations. Where Medicaid is involved, reimbursement and program structure may require additional attention through current Medicaid billing resources and Medicaid reimbursement guidance.
Complete authorization before scheduling creates irreversible financial exposure whenever possible. If emergency or urgent circumstances create exceptions, document the actual circumstances and follow applicable payer procedures.
Stage 3: Scheduling and Pre-Service Financial Clearance
Schedule the patient only after the team knows whether authorization is approved, pending, unnecessary, or requires escalation. Confirm the service fits the approved date range, units, provider, and location.
Financial clearance should also identify expected patient responsibility. Strong medical billing processes reduce the unpleasant situation in which the first serious financial conversation happens after the payer has processed the claim.
Stage 4: Documentation and Charge Capture
After the encounter, documentation must accurately describe what was performed. The clinical note, procedure report, medication administration record, operative documentation, or diagnostic report becomes the basis for medical coding.
Charge capture should also be reconciled with the authorization. If a surgeon planned one procedure but performed a materially different service, the billing team needs to determine whether the changed code affects authorization rather than mechanically sending the claim.
Stage 5: Coding and Compliance Review
Assign ICD-10-CM, CPT, and HCPCS coding from the documentation. Verify modifiers, units, diagnosis relationships, bundling considerations, and payer-specific requirements. These are the same capabilities required in outpatient coding, professional-fee coding, and more advanced coding audit roles.
Authorization staff and coders should have an escalation path when the authorized code differs from the code supported by the completed service. Quietly changing a claim to match the authorization despite contradictory documentation creates a compliance risk.
Stage 6: Claim Scrubbing and Submission
Run edits for demographics, provider identifiers, code relationships, modifiers, authorization information, payer-specific fields, and other claim requirements. Then transmit through an appropriate electronic claims submission platform.
Track acceptance at both clearinghouse and payer levels. A claim rejected before adjudication is different from a payer denial, and leaving clearinghouse rejections untouched can quietly inflate A/R.
Stage 7: Payment Posting and Contract Review
Post payments, adjustments, contractual allowances, patient responsibility, and denials correctly. Compare actual reimbursement with expected reimbursement using appropriate physician fee schedule guidance, payer contracts, or Medicaid reimbursement information.
An authorization number does not protect a practice from underpayment. Payment integrity still requires contract-aware review.
Stage 8: Denial and A/R Follow-Up
Categorize denials by root cause. Use the payer's remittance information and relevant CARC reference before deciding whether the claim needs correction, reconsideration, appeal, documentation, or another action.
Authorization-related denials should move to a specialized queue because the appeal often requires proof of approval, submission confirmation, clinical records, payer communication, and evidence that the billed service matched the authorization. A disciplined denial-management workflow protects these cases from becoming generic unpaid A/R.
Stage 9: Patient Balance and Final Resolution
Transfer patient responsibility only after payer processing is understood and the balance is valid. Do not automatically push a prior-authorization denial to the patient when payer contract terms, authorization records, or provider obligations indicate otherwise.
The final step is root-cause feedback. If the same authorization error appears repeatedly, the revenue-cycle team should repair the upstream process. That is how a billing operation becomes more reliable instead of simply becoming better at appealing preventable failures.
4. Prevent and Appeal Prior Authorization Denials Without Repeating the Original Error
Authorization denials should be categorized before anyone resubmits them. Repeatedly sending the same request with the same evidence wastes staff time and can consume appeal windows.
A medical-necessity denial requires comparison between payer criteria and the clinical documentation. Determine which criterion was not demonstrated. If the record actually supports it, identify the exact documentation and submit a focused reconsideration or appeal. If the documentation never established it, sending more copies of the same chart will rarely solve the problem. This is where coding-audit discipline, medical terminology knowledge, and professional coding judgment become useful outside pure code assignment.
An administrative denial may involve a missing referral, incorrect provider, invalid facility, incorrect member record, late request, exhausted visits, or an authorization that expired before treatment. These failures belong in front-end revenue-cycle analysis, not merely a generic denial-management queue.
A code mismatch denial deserves immediate comparison of the authorized code with the performed and billed service. Confirm that the claim was coded from the documentation. Then determine whether the authorization should have been amended. Altering accurate coding simply to reproduce the original authorization can create greater problems than the denial itself.
A no-authorization denial requires evidence. Search the authorization system, payer portal, attached documents, call references, submission confirmations, and approval records. If approval exists, appeal with the authorization number and service-match evidence. If authorization truly was never obtained, determine whether retroactive authorization is available under the payer's rules before writing off the account or shifting responsibility.
A timely-filing or appeal-deadline issue needs immediate escalation. A recoverable $20,000 claim approaching a payer deadline should outrank dozens of low-value balances with no immediate deadline. Billing teams should connect authorization work with claims-submission monitoring, CARC analysis, and formal insurance denial management.
Peer-to-peer review should also be controlled. When the payer offers clinical discussion, send the treating or reviewing clinician the denial reason, relevant policy criteria, submitted documentation, missing issue, deadline, and payer contact information beforehand. A physician discovering the case details during the call wastes a scarce opportunity.
Track overturns by denial reason. If 80% of one payer's authorization denials are ultimately overturned because the payer missed documentation already supplied, that pattern deserves payer escalation. If denials remain upheld because the practice consistently omits the same evidence, the internal process deserves correction.
For Medicare Advantage coordinated care plans, CMS rules include protections designed to reduce disruption: when a beneficiary undergoing an active course of treatment switches to a new MA plan, the new plan must provide a minimum 90-day transition period during which prior authorization cannot be required for that active treatment. CMS also requires an approved authorization for a course of treatment to remain valid for as long as medically reasonable and necessary under applicable criteria and circumstances. Understanding these distinctions can prevent staff from accepting an avoidable denial without examining the governing rule.

5. Build a Prior Authorization Control System That Measures Speed, Approvals, Denials, and Revenue Risk
A high-performing authorization department should be measurable. Counting “authorizations completed” is insufficient because a quick submission with a high denial rate can generate more downstream work than a slightly slower, complete request.
Track authorization requirement accuracy: how often staff correctly determine whether a service requires authorization. A high error rate creates both missed authorizations and unnecessary administrative work.
Track first-pass approval rate. This measures how often requests are approved without additional documentation, peer-to-peer intervention, reconsideration, or appeal. Low first-pass performance often points to poor clinical documentation, incorrect codes, or weak understanding of payer criteria.
Track submission-to-decision time by payer. This exposes payers or authorization categories that consistently delay scheduling. Under CMS's current rules, specified impacted payers face defined decision-time requirements for many medical-item and service requests beginning in 2026. A practice should still understand the exact program, request type, and applicable extension provisions before escalating a case.
Track requests for additional information. Categorize what the payer asks for: imaging, therapy history, medication trials, progress notes, laboratory results, diagnosis details, or other records. Repeated requests for the same missing element usually indicate an upstream documentation problem.
Track authorization-related claim denial rate. This is perhaps the most important measure because an authorization department can appear productive while the claims it supposedly cleared continue to deny.
Connect those denials with your CARC directory, denial-management process, electronic claims infrastructure, and medical billing system.
Track avoidable write-offs caused by authorization in dollars, not merely account count. Five authorization failures on expensive procedures may matter more financially than fifty low-dollar claim corrections.
Track authorization expiration loss. This should include procedures performed after an approval expired and unused authorizations that repeatedly require unnecessary resubmission because scheduling exceeded the valid period.
Track approved units remaining for recurring therapy, infusions, injections, rehabilitation, or other visit-limited services. A live unit balance can prevent a series of claims from being denied after the authorized quantity is exhausted.
Practices should also prepare for a more electronic prior-authorization environment. Under CMS-0057-F, impacted payers must implement Prior Authorization APIs that can expose covered items and services, documentation requirements, request and response functionality, approval details, denial reasons, and requests for more information beginning January 1, 2027.
That creates a practical technology question for every organization reviewing billing software or claim-submission platforms: Can the system integrate authorization requirements, submissions, statuses, and downstream claim data without forcing staff to re-key the same information across multiple portals?
CMS states that these electronic requirements in the 2024 rule focus on medical items and services and exclude drug prior authorizations; a separate 2026 proposal addresses drug-related electronic prior authorization. Because that drug rule is a proposal as of September 2026, practices should distinguish finalized requirements from proposed changes when designing workflows.
The final management goal is a closed feedback loop:
Eligibility → authorization requirement → complete clinical request → approval → scheduled service → correct coding → clean claim → payment → denial analysis → workflow correction.
When that loop works, authorization becomes part of revenue integrity rather than a disconnected administrative department. That same integration improves medical billing operations, strengthens coding compliance, reduces claim denials, and protects expected payer reimbursement.
6. FAQs About Prior Authorization and the Medical Billing Workflow
-
An approval confirms that the payer authorized a specified service under the applicable authorization process. Payment still depends on the final claim, eligibility, benefit coverage, medical necessity, provider participation, coding, units, modifiers, site of service, coordination of benefits, timely filing, and other payer rules.
That is why authorization should remain connected to medical coding, electronic claim submission, denial management, and reimbursement analysis. Treating the authorization number as a payment guarantee is one of the most expensive assumptions a revenue-cycle team can make.
-
At minimum, verify patient and plan information, ordering and rendering providers, facility, proposed service, CPT or HCPCS coding where applicable, diagnosis information, requested units, expected treatment dates, and supporting clinical evidence required by the payer.
The request should also preserve submission confirmation and case identifiers so the team can prove when and how the request was sent. Accurate CPT knowledge, reliable medical billing processes, and effective denial prevention all improve the quality of the request.
-
Start as soon as the ordered service, expected code, payer, location, and supporting clinical information are sufficiently known to submit a valid request. Waiting until the day before treatment gives the organization little room to resolve requests for additional records, denials, peer-to-peer reviews, provider changes, or scheduling problems.
Authorization lead time should therefore be built into the same scheduling design used for claims workflow, billing systems, and denial management. High-cost or clinically complex services deserve particularly strong controls.
-
First, code the performed service according to the documentation. Then determine whether the difference materially affects the authorization and whether the payer permits amendment, notification, or another correction.
The coding team should never select an unsupported code merely because it matches the authorization. Proper professional-fee coding, strong coding audit controls, and reliable claims submission require the billed service to remain faithful to the record.
-
A prior authorization denial occurs in the pre-service utilization-management process when the payer declines the requested approval. A claim rejection generally prevents a submitted claim from entering or completing adjudication because of structural, demographic, identifier, or other front-end problems. A claim denial occurs after adjudication when the payer refuses or reduces payment under applicable rules.
Those categories require different workflows. Use electronic claims resources for submission failures, CARC resources to interpret adjudicated adjustments, and denial-management processes for recovery and prevention.
-
For specified impacted payers under CMS-0057-F, prior-authorization decisions for applicable medical items and services generally must be sent within 72 hours for expedited requests and seven calendar days for standard requests beginning in 2026, subject to applicable program-specific rules and extensions.
The rule applies to defined CMS-regulated payer categories, so staff should verify whether the specific plan and request fall within its scope. Authorization teams should combine regulatory awareness with accurate insurance billing workflows, payer-denial tracking, and reliable claims systems.
