
Compliant Physician Query Templates: 25 Coding Query Examples
A physician query can resolve unclear documentation, protect coding accuracy, and strengthen the integrity of the health record, yet poor wording can create compliance exposure just as quickly. Coders working in professional-fee coding, inpatient coding, risk adjustment, and coding audits need queries that give providers genuine clinical choice. These 25 practical templates apply the 2026 AHIMA/ACDIS query guidance to specificity, conflicting documentation, cause-and-effect relationships, clinical validation, POA, procedures, and common documentation gaps.
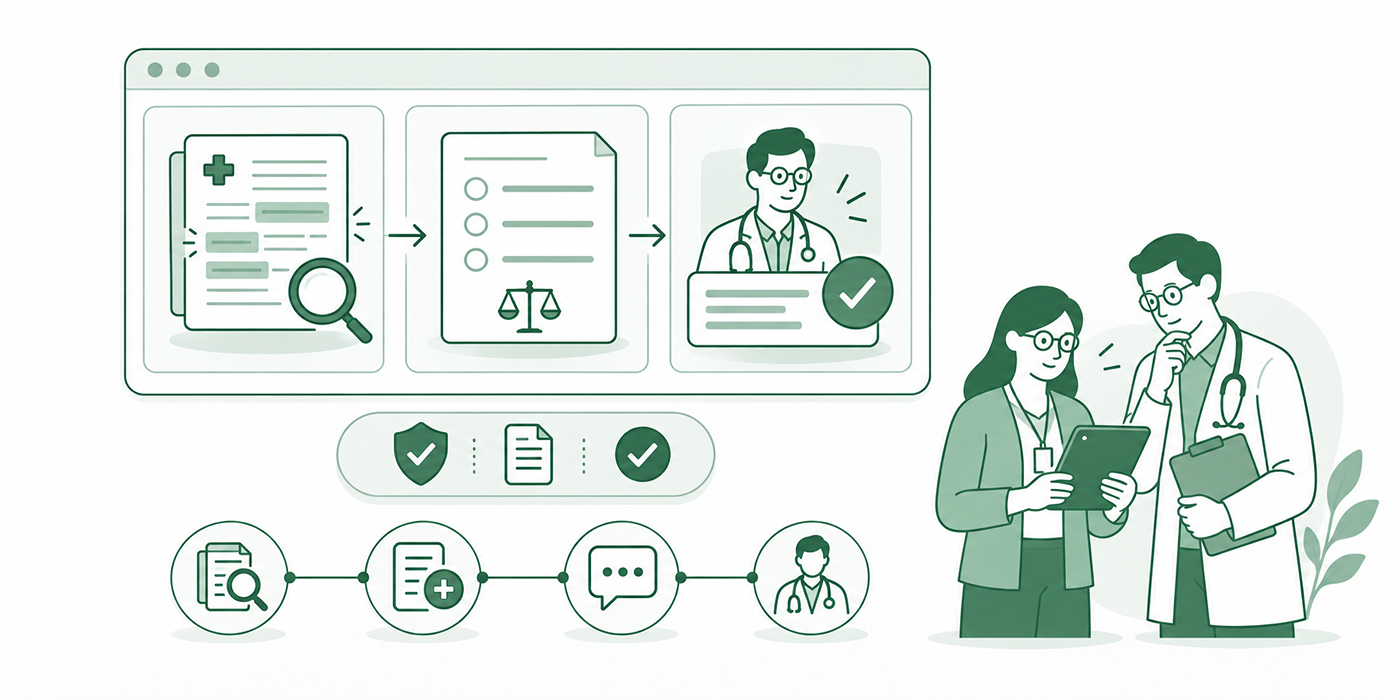
1. What Makes a Physician Query Compliant in 2026?
The standard changed recently enough that relying on an old query policy can create problems. The August 2026 AHIMA/ACDIS Guidelines for Achieving a Compliant Query Practice supersede every previous version, including the 2022 guidance, and apply across inpatient, outpatient, ambulatory, and professional-fee environments. That makes the updated guidance essential for anyone performing coding audits, developing professional-fee coding skills, reviewing risk-adjustment documentation, or preparing for medical coding interviews.
The current guidance identifies four core compliance principles: a query should be nonleading, contain clinically relevant and sourced indicators, exclude reimbursement or quality-impact language, and preserve independent provider judgment. The guidance also emphasizes substantial compliance with those core principles instead of treating every isolated formatting imperfection as evidence of a noncompliant query.
That distinction matters. A query can create concern even when it never explicitly tells the physician which diagnosis to select. The clinical indicators themselves can distort the decision if the query writer cherry-picks only evidence favoring one outcome. Likewise, a neutral-looking question can become problematic if its title says “Acute Respiratory Failure Query” before the physician even reads the case.
For coders working under high productivity expectations, handling denial management, interpreting claim adjustment reason codes, or preparing a defensible coding portfolio, a repeatable query checklist prevents shortcuts from becoming habits.
A compliant query should generally contain:
A neutral title, such as “Documentation clarification – respiratory status.”
The diagnosis, procedure, relationship, or documentation issue requiring clarification.
Patient-specific clinical indicators, with the source location identified.
Objective chart language without adding the query professional's clinical interpretation.
A clear question asking the provider to exercise clinical judgment.
Response options appropriate to the chosen query format.
An open alternative such as “Other explanation, please specify” when using multiple choice.
Authentication and retention according to organizational policy.
The 2026 guidance specifically says clinical indicators should identify where the information came from in the record. A heart rate of 120 should be presented as the recorded heart rate rather than relabeled by the query professional as “tachycardia.” Likewise, a hemoglobin result should be reproduced as documented rather than converted by the coder into a diagnosis. This principle is critical when moving from CPC exam preparation into production coding, pursuing higher-level coding specialties, or learning to defend decisions during coding interview assessments.
Query format also matters. Under the 2026 guidance:
Multiple-choice queries can be used in any circumstance when supported by relevant indicators. The provider must have an opportunity to give another explanation, and there is no mandated minimum number of diagnosis choices.
Yes/no queries are designed for clarification of an already documented diagnosis or relationship. They may address POA, confirmation of existing provider documentation, or a cause-and-effect relationship between documented conditions. They should not introduce a new diagnosis.
Open-ended queries can also be used in any circumstance. The 2026 guidance says they can be harder to interpret and therefore are not the preferred format, although they remain useful for complex situations and some verbal queries.
The ICD-10-CM Official Guidelines also direct coders to seek provider clarification in situations involving unclear relationships, conflicting documentation, and certain sequencing uncertainties. That connection makes query competence relevant to CCS preparation, CPT and coding principles, medical terminology skills, and eventual auditor responsibilities.
| Documentation Issue | Potential Query Trigger | Useful Starting Format | Compliance Check |
|---|---|---|---|
| Diagnosis lacks specificity | Specific detail affects valid code selection | Multiple choice | Offer only clinically supported choices |
| Acuity unclear | Acute/chronic status affects code | Multiple choice | Use encounter-specific evidence |
| Laterality missing | Documentation elsewhere suggests side | Multiple choice/open ended | Avoid assuming from procedure schedule alone |
| Conflicting diagnoses | Provider notes disagree materially | Multiple choice | Present relevant conflicting documentation |
| Cause-and-effect unclear | Two conditions documented without relationship | Yes/no or multiple choice | Both conditions must already be supported |
| Possible complication | Condition follows procedure or treatment | Yes/no | Occurrence after care alone does not establish causation |
| POA unclear | Timing cannot be established from record | Yes/no | Include “Unable to determine” |
| Pathology diagnosis absent from provider note | Pathologist documented definitive finding | Yes/no | Confirmation relates to existing diagnostic documentation |
| Radiology diagnosis needs confirmation | Diagnostic interpretation affects coding | Yes/no/multiple choice | Present the report accurately |
| Ancillary diagnosis documented | Dietitian, wound clinician, or other ancillary note contains relevant finding | Multiple choice | Ancillary note acts as an indicator |
| Clinical validation concern | Diagnosis exists with potentially inconsistent indicators | Multiple choice | Include relevant supporting and conflicting evidence |
| Problem-list diagnosis may be resolved | Current evidence indicates status may have changed | Multiple choice/yes-no | Ask for current status |
| Heart failure type unclear | Heart failure documented without sufficient type | Multiple choice | Use echo/provider evidence present in record |
| CKD stage unclear | CKD documented without current stage | Multiple choice/open ended | Use clinically relevant renal documentation |
| Pneumonia specificity | Documentation supports clarification of type or organism | Multiple choice | Avoid inventing organism from treatment choice |
| Respiratory condition lacks acuity | Provider documentation requires clarification | Multiple choice | List objective respiratory indicators |
| Anemia etiology unclear | Anemia documented with multiple possible causes | Multiple choice | Include only causes supported in chart |
| Encephalopathy specificity | General diagnosis documented | Multiple choice | Clinical evidence should support offered types |
| Malnutrition documentation gap | Nutrition assessment contains relevant findings | Multiple choice | Do not use yes/no solely from dietitian diagnosis |
| Pressure injury diagnosis unclear | Wound documentation requires provider clarification | Multiple choice | Distinguish permissible ancillary details from provider diagnosis |
| Sepsis documentation conflict | Diagnosis and clinical record appear inconsistent | Multiple choice | Include balanced clinical evidence |
| Principal diagnosis unclear | Two conditions potentially occasioned admission | Open ended/multiple choice | Do not reference DRG impact |
| Symptom etiology unclear | Workup identifies possible explanation | Multiple choice/open ended | Respect setting-specific uncertain diagnosis rules |
| Procedure approach missing | Operative details require clarification | Multiple choice | Use operative facts |
| Procedure extent unclear | Documentation cannot support precise procedural code | Open ended/multiple choice | Ask what was actually performed |
| PCS root-operation ambiguity | Operative objective cannot be determined | Multiple choice | Options should reflect supported procedural objectives |
| Device unclear | Implant/device changes code assignment | Multiple choice/open ended | Use operative and implant documentation |
| Historical condition appears active | Current encounter requires status clarification | Multiple choice | Especially important in risk adjustment |
| Condition status unclear | Active, resolved, history, or other status affects reporting | Multiple choice | Use current encounter evidence |
| Verbal clarification needed | Immediate documentation issue discussed with provider | Verbal query | Record indicators, question, response, participants, and date/time |
2. Physician Query Templates 1–13: Diagnosis, Specificity, Relationships and Clinical Validation
These are adaptable educational templates. Replace every bracketed item with patient-specific information actually documented in the record and follow organizational query policy. The same discipline supports accurate ICD-10 coding, stronger CPC coding skills, defensible medical coding interviews, and later coding-auditor work.
Template 1: Diagnosis Specificity
Clinical indicators: [Provider note/date] documents [diagnosis]. [Relevant study/note/date] documents [specific factual indicator].
Query: Based on your clinical judgment, please further specify the documented [diagnosis]:
[Supported specific diagnosis]
[Supported alternative]
Other explanation, please specify: ______
Unable to determine
This structure works well when additional specificity is supported and needed for accurate diagnosis coding or a coding assessment.
Template 2: Acute, Chronic, or Acute-on-Chronic Status
Clinical indicators: [Note/date] documents [condition]. Relevant documentation includes [objective indicator], [treatment], and [previous/current status].
Query: Please clarify the acuity of [condition] for this encounter:
Acute
Chronic
Acute on chronic
Other, please specify: ______
Unable to determine
Choose only options genuinely supported by the chart. This skill is valuable in inpatient coding, professional-fee coding, and medical coding interviews.
Template 3: Missing Laterality
Clinical indicators: [Provider note/date] identifies [condition]. [Imaging/procedure/other note] identifies [right/left/bilateral factual information].
Query: Please clarify the site/laterality of the documented [condition]:
Right
Left
Bilateral
Other, please specify: ______
Unable to determine
This is a straightforward query when laterality affects coding specificity and should be handled before the claim enters electronic submission.
Template 4: Conflicting Documentation
Clinical indicators: [Note/date] documents [diagnosis A]. [Another provider note/date] documents [diagnosis B]. Relevant findings include [objective facts].
Query: Please clarify the diagnosis that most accurately reflects the patient's condition for this encounter:
[Diagnosis A]
[Diagnosis B]
Other explanation, please specify: ______
Unable to determine
Conflicting documentation is a legitimate clarification trigger under official coding guidance. Resolving it early protects coding accuracy, denial management, and later audits.
Template 5: Cause-and-Effect Relationship
Clinical indicators: [Condition A] and [condition B] are documented in [source/date]. Relevant treatment/findings include [facts].
Query: Is [condition B] due to or associated with [condition A]?
Yes
No
Other relationship, please specify: ______
Unable to determine
The 2026 guidance permits yes/no queries to establish or negate a cause-and-effect relationship between already documented conditions. This distinction is especially important in coding audits and denial reviews.
Template 6: Possible Complication of Care
Clinical indicators: The patient underwent [procedure/treatment] on [date]. [Condition] is documented on [date]. Relevant facts include [symptoms/findings/intervention].
Query: Is the documented [condition] related to the [procedure/treatment]?
Yes
No
Other relationship, please specify: ______
Unable to determine
The ICD-10-CM guidelines place importance on provider documentation of the relationship between a condition and care when complication coding is involved. This is high-value knowledge for facility coders, auditors, and specialty coders.
Template 7: Present-on-Admission Status
Clinical indicators: [Condition] was documented on [date]. Admission documentation includes [relevant facts], while subsequent documentation includes [relevant facts].
Query: Was [condition] present at the time of inpatient admission?
Yes
No
Unable to determine
For a POA yes/no query, the 2026 AHIMA/ACDIS guidance specifically requires “Unable to determine” as an option. This belongs in the skill set of anyone studying inpatient coding or preparing for CCS coding questions.
Template 8: Pathology Finding Requiring Provider Confirmation
Clinical indicators: [Pathology report/date] documents [finding]. [Treating provider documentation] references [related condition/workup].
Query: Based on your review and clinical judgment, does the pathology finding represent [already documented pathology diagnosis]?
Yes
No
Other explanation, please specify: ______
Unable to determine
The current guidance permits yes/no clarification when substantiating an already documented medical diagnosis from qualifying provider documentation such as pathology. The distinction helps in professional coding and coding interview scenarios.
Template 9: Radiology Finding Requiring Clarification
Clinical indicators: [Radiology report/date] states [verbatim relevant finding]. [Provider note/date] documents [related symptoms/diagnosis].
Query: Based on your clinical judgment and review of the diagnostic findings, please clarify the condition represented during this encounter:
[Clinically supported condition]
[Supported alternative]
Other explanation, please specify: ______
Unable to determine
Keep the radiologist's actual wording intact where possible. That discipline improves medical coding accuracy, strengthens coding portfolios, and helps with audit defense.
Template 10: Ancillary Documentation Supporting Clarification
Clinical indicators: [Dietitian/wound-care/nursing/therapy note/date] documents [objective findings]. [Provider note/date] documents [related condition or concern].
Query: Based on the clinical indicators and your professional judgment, please clarify the diagnosis associated with these findings:
[Supported diagnosis]
[Supported alternative]
Other explanation, please specify: ______
Unable to determine
The 2026 guidance specifically cautions against using a yes/no query based solely on a diagnosis documented by an ancillary clinician who lacks authority to establish that medical diagnosis. Multiple choice should be used in those circumstances. This rule matters in risk-adjustment coding and facility coding.
Template 11: Clinical Validation of an Existing Diagnosis
Clinical indicators: [Provider note/date] documents [diagnosis]. The record contains [relevant supporting indicator], [potentially conflicting indicator], [treatment], and [trend].
Query: Based on the patient's clinical picture, please clarify the status of the documented [diagnosis]:
Diagnosis remains clinically supported
Diagnosis ruled out/resolved
Other explanation, please specify: ______
Unable to determine
Balanced indicators are crucial. A query built only from facts supporting removal or addition of a diagnosis can distort provider judgment. Clinical validation skills become especially valuable in coding auditor careers, risk adjustment, and high-accuracy coding environments.
Template 12: Problem-List Condition Status
Clinical indicators: The active problem list contains [condition] dated [date]. Current encounter documentation shows [relevant current findings/status].
Query: Please clarify the current status of [condition]:
Active
Resolved
History of condition
Other status, please specify: ______
Unable to determine
This template is particularly valuable for risk-adjustment coders, where blindly carrying forward conditions can create compliance exposure, and for professional-fee coders reviewing longitudinal records.
Template 13: Uncertain Diagnosis Near Inpatient Discharge
Clinical indicators: [Earlier note/date] documents “possible/probable/suspected [condition]”. Clinical evaluation includes [tests], [treatment], and [monitoring]. The discharge documentation does not clearly address the condition.
Query: Based on your clinical judgment at discharge, please clarify the status of [condition]:
[Supported final diagnosis]
Condition remains uncertain as clinically documented, if applicable under inpatient reporting rules
Condition ruled out
Other explanation, please specify: ______
Unable to determine
The 2026 guidance permits carefully supported clarification involving uncertain inpatient diagnoses and recommends sparing use. Candidates studying CCS coding, inpatient coding careers, and coding audit work should understand this setting-specific issue.
3. Physician Query Templates 14–25: Common Clinical, Sequencing and Procedure Clarifications
Template 14: Heart Failure Specificity
Clinical indicators: [Provider note/date] documents heart failure. [Echo/date] documents [relevant findings]. Treatment/current status includes [factual information].
Query: Please further specify the documented heart failure:
[Clinically supported type/acuity]
[Clinically supported alternative]
Other explanation, please specify: ______
Unable to determine
Use options supported by this patient's chart. This approach strengthens ICD-10 reasoning, medical terminology interpretation, and coding interview performance.
Template 15: CKD Stage
Clinical indicators: [Provider note/date] documents chronic kidney disease. Relevant renal documentation includes [lab trends/date], [nephrology documentation/date], and [treatment].
Query: Please clarify the current stage/status of the documented CKD:
[Supported stage]
[Other supported stage/status]
Other, please specify: ______
Unable to determine
Do not convert a laboratory result into the diagnosis yourself. This is exactly the boundary coders must understand in risk adjustment, coding audits, and medical coding interviews.
Template 16: Pneumonia Specificity
Clinical indicators: [Provider note/date] documents pneumonia. Relevant documentation includes [imaging], [culture/testing], [symptoms], and [treatment].
Query: Please clarify the type/etiology of the documented pneumonia:
[Supported type]
[Supported alternative]
Other explanation, please specify: ______
Unable to determine
Antibiotic choice alone should never become the coder's diagnosis. Reliable abstraction matters in inpatient coding, coding productivity environments, and denial prevention.
Template 17: Respiratory Condition Acuity/Specificity
Clinical indicators: [Provider documentation/date] states [respiratory condition]. The chart records [oxygen requirement], [documented baseline], [objective findings], and [treatment].
Query: Please clarify the patient's respiratory diagnosis/status:
[Clinically supported option]
[Clinically supported alternative]
Other explanation, please specify: ______
Unable to determine
Use the actual recorded oxygen values and provider documentation without turning raw values into your own diagnosis. This is valuable for CCS candidates and future auditors.
Template 18: Anemia Etiology
Clinical indicators: [Provider note/date] documents anemia. Relevant documentation includes [laboratory trend], [bleeding status], [underlying disease/treatment], and [therapies].
Query: Please clarify the etiology/type of the documented anemia:
[Supported cause/type]
[Supported alternative]
Other explanation, please specify: ______
Unable to determine
Use only etiologies supported by the encounter. This kind of reasoning differentiates strong coding interview candidates, competent facility coders, and future coding auditors.
Template 19: Encephalopathy Specificity
Clinical indicators: [Provider note/date] documents encephalopathy. Relevant documentation includes [neurologic findings], [underlying conditions], [testing], and [treatment].
Query: Please further specify the documented encephalopathy:
[Supported type]
[Supported alternative]
Other explanation, please specify: ______
Unable to determine
Specificity should come from the provider's clinical judgment. That principle runs through CPC coding preparation, CCS case practice, and production coding audits.
Template 20: Malnutrition Clarification
Clinical indicators: [Nutrition assessment/date] documents [objective findings and assessment]. Provider documentation includes [relevant diagnosis/clinical status]. Treatment includes [nutrition intervention].
Query: Based on the documented clinical indicators and your professional judgment, please clarify the patient's nutritional diagnosis:
[Supported diagnosis]
[Supported alternative]
Other explanation, please specify: ______
Unable to determine
The 2026 guidance specifically uses ancillary clinician documentation as potential clinical evidence while preserving provider responsibility for the diagnosis. This is essential for facility coding, clinical validation, and denial defense.
Template 21: Principal Diagnosis Clarification
Clinical indicators: The patient was admitted for [presentation]. Documentation includes [condition A] in [source/date] and [condition B] in [source/date]. Relevant evaluation/treatment includes [facts].
Query: Based on your clinical judgment after study, please clarify the condition chiefly responsible for the admission:
[Condition A]
[Condition B]
Other condition, please specify: ______
Unable to determine
Exclude DRG, reimbursement, severity-weight, or quality language from the query. The 2026 guidance explicitly excludes reimbursement and reporting-impact information from compliant queries. This is fundamental knowledge for inpatient coders and coding auditors.
Template 22: Symptom Etiology
Clinical indicators: The patient presented with [symptom]. Workup includes [testing/findings]. Provider documentation references [possible explanations].
Query: Based on your clinical judgment, please clarify the condition responsible for [symptom] during this encounter:
[Supported diagnosis]
[Supported alternative]
Symptom remains unexplained
Other explanation, please specify: ______
Unable to determine
Setting-specific uncertain-diagnosis rules still govern code assignment. This distinction is tested frequently in coding interviews, CPC practice questions, and CCS preparation.
Template 23: Historical Diagnosis Versus Active Condition
Clinical indicators: Previous documentation dated [date] identifies [condition]. Current documentation includes [treatment/status/findings].
Query: Please clarify the current status of [condition] for this encounter:
Active/current
History of condition
Resolved
Other status, please specify: ______
Unable to determine
This template is especially useful in HCC and risk-adjustment coding, where current documentation must support appropriate condition capture, and in auditing roles.
Template 24: Procedure Approach or Technique
Clinical indicators: Operative note dated [date] documents [procedure]. The report contains [relevant operative details], while the approach/technique required for code assignment remains unclear.
Query: Please clarify the approach/technique used for [procedure]:
[Supported approach]
[Supported alternative]
Other, please specify: ______
Unable to determine
Procedure-specific queries become particularly important in facility coding, inpatient coding, and CCS-level coding.
Template 25: Procedure Objective / ICD-10-PCS Clarification
Clinical indicators: The operative note dated [date] documents [procedure description]. The report states [relevant operative actions], but the procedural objective needed for code assignment remains ambiguous.
Query: Based on the procedure performed, please clarify the operative objective:
[Clinically supported procedural objective]
[Supported alternative objective]
Other, please specify: ______
Unable to determine
This query should focus on what the surgeon actually performed and avoid presenting a preferred PCS root operation simply because one produces a different DRG. That distinction is central to inpatient coding, coding auditor development, CCS preparation, and advanced coding specialties.
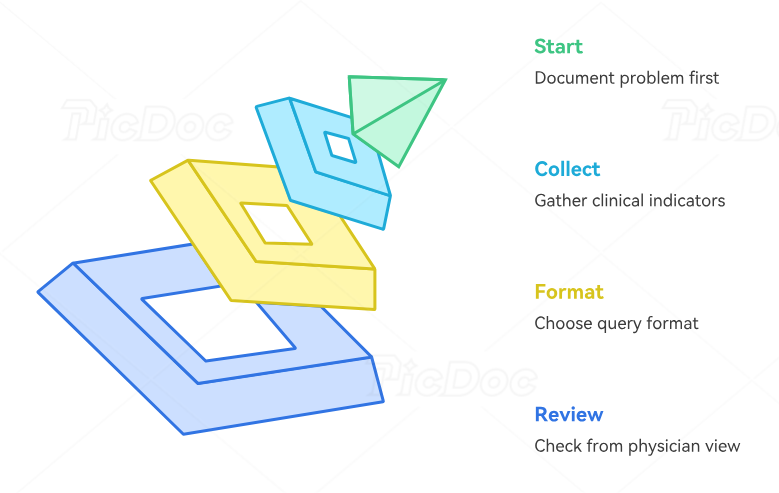
4. How to Build a Compliant Query From the Chart Instead of From the Code You Want
The safest workflow begins with the documentation problem. Start by asking what remains unclear in the health record. A coder working on professional-fee claims, reviewing risk-adjustment conditions, handling denials, or preparing for a coding audit should be able to state the gap in one sentence before drafting anything.
For example:
Documentation gap: Heart failure is documented, while the record contains information that may permit the provider to specify its type.
That starting point is safer than building the query backward from a target code.
Next, collect the minimum clinically relevant indicators required to explain why clarification is reasonable. The 2026 guidance places no universal numerical requirement on clinical indicators because appropriate evidence varies by patient and diagnosis. A five-indicator minimum can therefore become just as artificial as a one-indicator maximum. Coders preparing for medical coding interview tests, auditor positions, or high-productivity environments need judgment here.
Source each indicator. A useful format is:
Echocardiogram, 9/11: [relevant documented finding]
Cardiology note, 9/12: “heart failure”
Medication administration record, 9/12: [relevant treatment]
This lets the physician inspect the source quickly and makes the query easier to defend during a later coding audit, denial review, or reimbursement dispute involving the physician fee schedule.
Then select the format.
Use multiple choice when clinically supported possibilities can be presented clearly. Under the 2026 guidance, multiple choice can be used in any circumstance, answer choices should remain clinically relevant, and the provider must have an opportunity to provide an alternative explanation.
Use yes/no when clarifying an already documented diagnosis, POA status, or an established question of relationship between documented conditions. The current guidance explicitly prohibits using yes/no to introduce a previously undocumented diagnosis. This is a highly testable distinction for candidates studying CPC coding principles, CCS cases, or coding interview scenarios.
Use open ended when the clinical picture is complex or useful response options cannot be framed cleanly. Open-ended queries remain permissible under the 2026 standard, although the guidance says they can be difficult to interpret and are therefore not the preferred format.
Finally, review the finished query from the physician's perspective. Remove language that reveals a desired answer. Remove reimbursement consequences. Remove quality-score consequences. Remove artificial emphasis such as bolding one answer choice. The 2026 guidance specifically cautions against answer-option highlighting, arrows, underlining, and other emphasis capable of signaling a preferred response.
That final preflight is particularly important for coders who work under accuracy quotas, move into coding auditing, specialize in HCC coding, or handle documentation associated with claim denials.
5. Eight Query Compliance Traps That Can Turn a Good Template Into a Bad Query
1. Copying clinical indicators from a template without checking the patient. Templates create efficiency, but each query must reflect the actual encounter. A copied laboratory value, unsupported diagnosis option, or irrelevant treatment weakens the entire query. This matters especially in high-volume coding jobs, where speed pressures can encourage unsafe shortcuts.
2. Putting the desired diagnosis in the title. A title such as “Acute Respiratory Failure Query” can influence the provider before the evidence is reviewed. The 2026 guidance explicitly addresses query-title neutrality. Use neutral titles tied to the documentation domain, especially in risk adjustment and auditing.
3. Translating raw findings into diagnoses. If the chart says heart rate 120, reproduce that fact. The query writer should avoid relabeling it with a diagnostic interpretation the provider has not made. The same principle applies when interpreting laboratory results, imaging, medication choices, and treatment intensity. This boundary belongs among the core skills tested in coding interviews and CCS preparation.
4. Using a yes/no query to create a new diagnosis. Current guidance limits yes/no to specific clarification uses involving existing documentation or relationships. When the diagnosis has never been documented, choose another compliant format. This becomes especially important for HCC coders and coders moving into audit work.
5. Filling multiple-choice lists with irrelevant diagnoses. Older training sometimes encouraged long lists purely to make the query appear neutral. The 2026 guidance focuses on clinically relevant options supported by the record and says there is no required minimum number of choices. A shorter evidence-based list can therefore be more compliant than a long collection of implausible possibilities.
6. Mentioning money, DRGs, quality scores, or denial impact. The query should resolve documentation. The current guidance expressly excludes reimbursement, quality measures, denial mitigation, and other reporting impacts from the clarification request. Keep those operational concerns outside the provider-facing query even when the documentation later affects physician reimbursement, Medicaid reimbursement, or denial management.
7. Treating verbal queries as informal conversations that leave no trail. The 2026 guidance says verbal queries concerning a specific encounter must follow compliant-query principles, with relevant information recorded and the response documented in the permanent health record for coding purposes. It specifies documenting participants, date/time, clinical indicators and sources, the clarification statement, any options given, and the provider's response. That matters in remote coding roles, professional-fee environments, and audits.
8. Building templates once and leaving them untouched for years. Query guidance changes. The August 2026 update replaced the 2022 version, illustrating why organizations need periodic review, education, and auditing. Coders should keep current through continuing education resources, current coding exam resources, auditor training, and updated coding interview preparation.
A useful internal audit can sample queries monthly and score them across reason for query, clinical-indicator sourcing, balance, title neutrality, response-option design, absence of financial influence, provider authentication, and record retention. Track errors by category rather than producing one overall compliance percentage. That allows leaders to distinguish a training problem from a template-design problem, EHR configuration issue, or individual workflow error.
This type of structured review prepares coders for medical coding auditor careers, reduces avoidable coding stress, strengthens denial defense, and develops the reasoning employers look for in medical coding interviews.
6. FAQs About Compliant Physician Queries
-
Yes. The 2026 AHIMA/ACDIS guidance says the multiple-choice format can be used in any circumstance when the statement is nonleading and response options are supported by relevant clinical indicators. The provider must be able to supply an alternative explanation, such as through an “Other, please specify” option. There is no required minimum number of diagnosis choices. This is important knowledge for CPC-trained coders, CCS candidates, risk-adjustment coders, and coding auditors.
-
The current guidance allows yes/no queries for clarification of an already documented diagnosis, POA status, confirmation of qualifying existing diagnostic documentation, and cause-and-effect relationships between documented conditions. A yes/no query should not be used to introduce a new diagnosis. Understanding that boundary helps during medical coding interview tests, facility coding, professional-fee coding, and audit reviews.
-
The 2026 guidance identifies “unable to determine” as an option that may be appropriate depending on the circumstances. POA yes/no queries specifically require it. Multiple-choice queries must provide a route for another explanation, such as “Other, please specify.” Query writers should build response options around the clinical situation and organizational policy rather than mechanically inserting identical options into every template. This judgment becomes important in coding audits and high-productivity coding work.
-
Yes, when the prior information is clinically relevant to the current encounter. The 2026 guidance permits relevant prior-record evidence to support a query while emphasizing that code assignment for the current encounter is not simply based on documentation from a previous encounter. This distinction is especially important in risk adjustment coding, professional-fee coding, and longitudinal coding audits.
-
Yes. The 2026 guidance permits recognized clinical definitions or diagnostic criteria to appear within a template when appropriately sourced. The criteria should appear without visual or textual signals suggesting a preferred response. This can be useful for complex clinical validation, risk-adjustment coding, and specialty coding.
-
The 2026 guidance says that when a compliant query has been properly answered, authenticated by the responsible provider, and incorporated into the permanent health record, the response can support code assignment without being repeated elsewhere. Organizations should define approved query-response locations in policy. This detail matters for coding compliance, claims workflows, and later denial review.
