
How to Create a Personalized Medical Coding Study Guide
A strong medical coding study guide should behave like a diagnostic system rather than a stack of notes. Your plan needs to identify exactly where you lose accuracy, which code families slow you down, what reference material you fail to navigate efficiently, and which mistakes repeat under time pressure. Someone preparing through self-study, community college, or a coding bootcamp will need a different plan from a career changer with no healthcare background, a repeat test-taker rebuilding after failing the CPC exam, or an experienced biller moving deeper into coding.
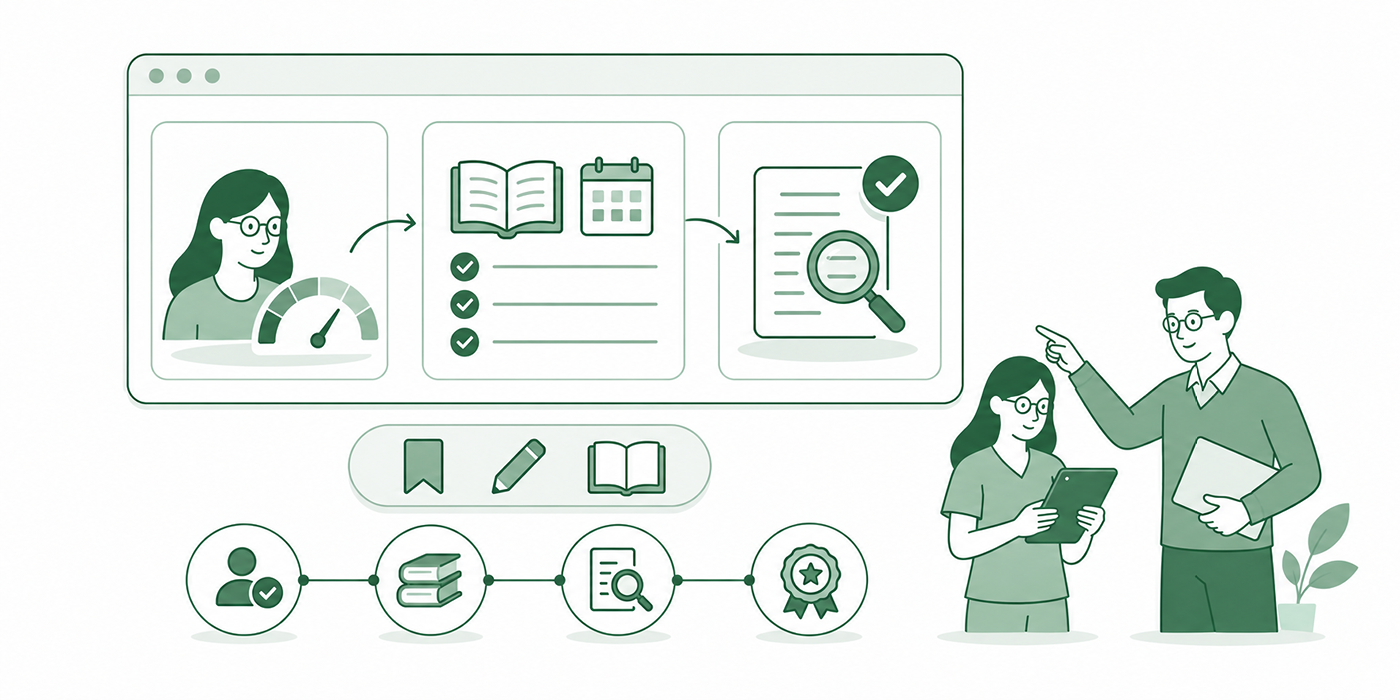
1. Build Your Medical Coding Study Guide From Your Weaknesses, Not the Textbook Order
The fastest way to waste study hours is to study every topic equally. Medical coding exams and real coding work expose uneven skill profiles: one learner may understand anatomy but repeatedly misuse modifiers, while another can identify the diagnosis quickly yet loses time navigating CPT. A third student may understand individual codes while struggling to connect documentation, sequencing rules, and payer logic.
Start with a baseline diagnostic assessment before building your schedule. Use 25–50 mixed questions from a reliable question bank such as AMBCI's CPC exam questions with detailed explanations. Complete them under moderate time pressure and record more than right or wrong. Track whether each miss came from knowledge, code-book navigation, terminology, anatomy, guideline interpretation, sequencing, modifier selection, or rushing.
Students working toward CPC can combine that baseline with a structured CPC exam study strategy, while learners still deciding where to study should compare the actual workload and employer value of coding training options before buying additional materials. Spending more rarely fixes a badly designed study process, which is why understanding training costs and return on investment matters before adding another course.
Use a simple 0–3 mastery score:
0: You cannot solve the problem without reading the answer.
1: You recognize the concept but frequently choose the wrong code or rule.
2: You usually solve it correctly but work too slowly or need repeated verification.
3: You solve it accurately, explain your reasoning, and locate the supporting rule efficiently.
This scoring method turns vague statements such as “I am bad at surgery coding” into a measurable weakness. It also prevents learners from repeatedly studying comfortable material because it feels productive.
Your guide should also distinguish knowledge weakness from execution weakness. If you understand E/M concepts but cannot find relevant instructions quickly, another hour of passive reading may add little. Navigation drills are more useful. If you repeatedly misunderstand clinical language, spend time strengthening medical terminology for coding. If nervousness destroys otherwise strong scores, incorporate an exam-anxiety management plan instead of treating every low mock score as a content deficiency.
Personalized Medical Coding Study Guide Builder: 30 Skills to Audit
| Skill Area | What You Must Be Able to Do | Warning Sign | Personalized Study Action |
|---|---|---|---|
| Medical terminology | Decode unfamiliar clinical terms | You guess from keywords | Build root, prefix, and suffix drills |
| Anatomy | Identify body systems, sites, laterality, and relationships | Wrong site leads to wrong code family | Review anatomy by coding chapter |
| Documentation reading | Separate clinically relevant facts from noise | Long notes overwhelm you | Practice extracting diagnosis, service, site, approach, and status |
| ICD-10-CM index use | Find the correct starting term | You search randomly | Run timed index-location drills |
| Tabular verification | Confirm instructions after index lookup | You stop at the index | Require tabular confirmation on every diagnosis drill |
| Sequencing | Determine primary and additional diagnoses correctly | Correct codes appear in wrong order | Create sequencing-only case sets |
| Combination codes | Recognize when one code captures multiple elements | You overcode conditions | Build a combination-code error log |
| Laterality | Capture right, left, bilateral, or unspecified correctly | You lose easy accuracy points | Highlight laterality during documentation extraction |
| 7th characters | Apply encounter and healing extensions correctly | You confuse initial and subsequent care | Use scenario-based extension drills |
| Excludes notes | Interpret exclusion instructions accurately | Conflicting diagnoses get reported together | Create a notes-and-conventions review sheet |
| CPT structure | Navigate sections, subsections, notes, and code families | You know the service but cannot locate it efficiently | Practice code-family navigation |
| E/M | Apply applicable E/M rules to documentation | Levels are chosen by intuition | Work cases with written reasoning |
| Surgery coding | Identify procedure, approach, site, and bundled components | Operative reports take excessive time | Break reports into procedural elements |
| Radiology | Distinguish services and supervision/interpretation concepts | Similar services blur together | Create comparison drills |
| Pathology/lab | Recognize test and service categories | You rely on memorized code fragments | Study service families instead of isolated numbers |
| Medicine section | Distinguish closely related services | You skip instructional notes | Annotate decision points |
| Modifiers | Explain why a modifier is required | You choose modifiers by pattern recognition | Build modifier decision scenarios |
| HCPCS Level II | Locate supplies, equipment, drugs, and services | HCPCS questions take too long | Practice alphabetic and table navigation |
| Bundling logic | Recognize services that may be integral | You report every documented service separately | Add bundling checks to every procedure case |
| Professional vs facility coding | Understand how coding context changes | You apply one workflow everywhere | Compare matched professional and facility examples |
| Inpatient vs outpatient logic | Recognize different coding environments | You mix rule sets | Maintain separate rule summaries |
| Billing workflow | Understand how coding affects claims and reimbursement | Codes feel disconnected from revenue cycle consequences | Map code decisions to claim outcomes |
| Denials | Recognize common coding-related denial causes | You cannot explain downstream impact | Review denial examples alongside coding errors |
| Payer adjustments | Interpret adjustment reasons in billing context | Remittance logic is unfamiliar | Practice with adjustment-reason references |
| Code-book navigation speed | Locate supporting rules efficiently | Correct answers take too long | Run 10-minute navigation sprints |
| Question interpretation | Identify what the question is actually testing | You solve the wrong problem | Write the tested concept before reviewing answers |
| Elimination strategy | Discard choices using code logic | Two answers constantly seem plausible | Record why each rejected option is wrong |
| Time management | Protect time for difficult cases | Early questions consume the session | Use checkpoint-based timed sets |
| Error analysis | Find the cause behind every miss | You only record your score | Maintain a categorized error ledger |
| Retention | Recall rules after several days | Material feels familiar but cannot be retrieved | Schedule spaced mixed review |
2. Turn the Diagnostic Results Into a Personalized Weekly Study Plan
Once weaknesses are scored, convert them into a weighted schedule. Give the most study time to topics that combine low mastery, high frequency, and slow execution. Someone scoring 0 in modifiers and 2 in terminology should usually allocate more time to modifiers than terminology, even if terminology feels easier to review.
A practical weekly allocation might look like this:
40% weak-area correction. Work on topics scoring 0–1. Use active cases, reference navigation, and written reasoning. Students preparing for CPC can pull targeted exercises from a CPC preparation stack and compare their approach with strategies designed to pass the CPC on the first attempt.
25% mixed coding practice. Mixing diagnosis, CPT, HCPCS, modifiers, and documentation forces your brain to identify the required rule rather than relying on the chapter heading. This matters because actual assessments and workplace charts do not announce which weakness is about to be tested.
20% timed application. Speed should be trained after reasonable accuracy exists. Learners who immediately chase charts-per-hour can develop careless habits similar to the pressure described in real-world medical coding productivity quotas. Measure both accuracy and time so faster work never hides deteriorating decision quality.
10% spaced review. Revisit errors after 24 hours, several days, and again the following week. Reviewing the answer immediately creates familiarity; delayed retrieval tests whether the knowledge is usable.
5% reference maintenance. Update your tabs, notes, bookmarks, and quick-reference pages as permitted by the rules of your course or examination. Keep your system lean. Excessive annotations can become another search problem.
Career context should influence your study mix as well. A learner targeting inpatient versus outpatient coding needs different depth from someone deciding between professional-fee and facility coding. Someone interested in risk adjustment coding should eventually develop deeper diagnosis-documentation reasoning, while a future medical coding auditor will need unusually strong guideline interpretation and defensible reasoning.
Your study calendar should therefore answer three questions every day: What weakness am I correcting? What evidence will prove improvement? When will I test it again? “Study CPT for two hours” is vague. “Complete 15 mixed modifier cases, explain every miss, then retest the missed concepts Friday” produces measurable progress.
3. Use an Error Log That Tells You Exactly Why You Keep Missing Questions
Your error log is the highest-value document in a personalized study guide. A score tells you how often you were wrong. An error log tells you why you were wrong and what needs to change.
For every missed question, record:
Topic → Your answer → Correct answer → Root cause → Supporting rule → Prevention rule → Retest date.
The root-cause field is critical. Use precise categories such as:
knowledge gap
terminology gap
anatomy gap
wrong index term
tabular instructions missed
modifier misuse
sequencing error
documentation detail overlooked
bundled service reported separately
question misread
time-pressure guess
answer changed without evidence
Students who have failed the CPC exam especially need this level of diagnosis. Simply retaking more practice questions can reproduce the same mistakes at higher volume. A better second attempt isolates recurring failure patterns and connects them with a deliberately revised CPC study plan.
Track error recurrence as well. A modifier mistake that appears once may be a lapse. The same reasoning failure appearing five times indicates a system problem. Move recurring errors into a “must-fix” queue and retest them through unfamiliar examples rather than memorizing the original question.
This method also prepares you for employment. Coding interviews can include practical assessments, so understanding your reasoning matters beyond certification. Reviewing common medical coding interview tests can help you shift from answer memorization to defensible application. Once certified, that reasoning should also appear as credible proof of skill on a medical coding resume.
Billing knowledge can strengthen the same process. When you understand the claim consequence of coding errors, abstract rules become operational. Use resources on claim adjustment reason codes, insurance denial management, and electronic claims submission platforms to see how weak coding can surface later as rejected, adjusted, delayed, or underpaid claims.
4. Study Medical Coding Through Active Retrieval, Code-Book Navigation, and Cases
Passive study feels efficient because reading creates recognition. Coding requires retrieval, navigation, interpretation, and decision-making. Your personalized guide should therefore be dominated by things you must do, rather than pages you intend to reread.
Use a four-step practice cycle:
Step 1: Retrieve before reviewing
Before reopening notes, write what you remember about a rule or coding concept. Then compare your recall with the source material. This exposes knowledge that feels familiar but cannot be independently retrieved.
For foundational gaps, combine retrieval with focused work on medical terminology, structured CPC exam preparation, and well-explained CPC practice questions.
Step 2: Navigate instead of memorizing code numbers
Train yourself to locate the right family, follow instructional notes, verify the code, and explain your selection. Memorizing thousands of code numbers is a poor substitute for knowing how the classification system directs you toward the correct answer.
Students exploring other credentials should apply the same principle when comparing CCS certification programs or CBCS certification courses. The study system should match the credential's tested knowledge and the kind of work you eventually want to perform.
Step 3: Convert rules into cases
If you learn a modifier, diagnosis convention, or sequencing rule, immediately apply it to multiple cases. Change the documentation details between cases. Ask what new fact would change the answer.
That “counterfactual” technique is powerful because it makes you identify the decision boundary. Instead of remembering that Case A used a certain modifier, you learn exactly which documentation fact justified it.
Anyone considering a specialty can make cases increasingly career-specific. Compare surgical, emergency, cardiology, inpatient, and audit-oriented work using AMBCI's guide to higher-paying coding specialties. Career changers can also see how prior clinical exposure transfers through pathways such as medical coding after nursing and medical coding after medical assisting.
Step 4: Explain every answer
After difficult questions, state the reasoning in one or two sentences. If you cannot explain why an answer is correct, your knowledge may still depend on recognition.
This is especially useful for learners planning to work remotely or independently. Medical coding jobs often measure accuracy alongside throughput, and understanding coding stress, audits, denials, and productivity pressure helps students appreciate why defensible decisions matter. Learners seeking quieter roles can also explore medical coding jobs with fewer phone calls while building the technical independence those positions often require.

5. Measure Progress With Accuracy, Speed, Retention, and Job Readiness
A personalized study guide needs four scoreboards, because a single practice-test percentage hides too much.
Accuracy
Track your overall percentage and category-level percentage. If your overall score rises while surgery accuracy stays flat, you still have a concentrated weakness.
Speed
Measure time per question or case, preferably by topic. Slow but accurate performance often signals weak navigation, excessive second-guessing, or poor familiarity with code-family structure. High speed with poor accuracy usually indicates premature guessing.
This distinction matters when preparing for workplaces where productivity quotas coexist with auditing and quality review.
Retention
Retest previously mastered concepts after several days. A topic deserves a high mastery score only if performance survives a delay. Your study guide should automatically recycle deteriorating topics into the next week's priority list.
Transfer
Ask whether you can apply the concept to a new case. Transfer is more valuable than memorizing the exact pattern used in your course.
This becomes crucial when transitioning from certification into employment. New coders frequently discover that passing an exam and winning a first coding role are separate problems. Study the hiring patterns discussed in best employers for new medical coders, strengthen your post-certification coding resume, and rehearse the kind of reasoning seen in coding interview assessments.
Your guide should also contain stop rules. If a topic remains above your accuracy target across several mixed, delayed reviews, reduce its study allocation. Redirect that time toward weaker material. Personalization means the plan must change when your performance changes.
Avoid endlessly buying resources. A learner who owns five courses and finishes none may benefit more from consolidating around one curriculum, one question bank, one error log, and current reference materials. Review the trade-offs behind coding education spending and compare available online CPC programs before paying for another overlapping product.
Finally, rehearse the endgame. In the final stage of preparation, use complete mixed sets, realistic time constraints, deliberate break and pacing strategies, and a detailed medical billing and coding exam-day checklist. If anxiety changes your performance, treat it as a trainable variable through coding exam-anxiety preparation, rather than waiting until exam morning to manage it.
6. FAQs About Creating a Personalized Medical Coding Study Guide
-
The useful number depends on your baseline, target credential, deadline, and retention. Ten focused hours built around active coding can outperform twenty hours of passive videos and rereading. Start by completing a diagnostic using CPC-style practice questions, then estimate how many weak areas require correction.
Someone entering coding with no prior healthcare background may need additional anatomy and terminology work. Someone transitioning from medical assisting into coding may already possess useful clinical vocabulary and documentation familiarity.
-
Yes, when separating them reduces search time. Build concise rule sheets organized around decision points, exceptions, conventions, and recurring mistakes. Avoid rewriting entire chapters.
Your diagnosis notes should emphasize navigation, conventions, sequencing, and documentation requirements. CPT notes should emphasize code-family logic, instructions, modifiers, and bundling considerations. HCPCS notes should focus on categories that repeatedly slow you down. Tie each section back to your CPC study strategy rather than building an enormous reference binder that you rarely retrieve from memory.
-
Stop taking full practice tests for several days and inspect the errors underneath the score. Identify the two or three root causes producing the largest number of misses. Run focused drills, retest those concepts through new examples, then return to mixed questions.
Students repeating the same weaknesses should study the patterns commonly seen after a failed CPC attempt. If timing rather than knowledge is the bottleneck, use the leaner methods in AMBCI's 2026 CPC preparation guide.
-
Learning enough billing to understand the revenue-cycle consequences of coding decisions can make the material more meaningful. You do not need to master every billing function before learning coding.
Useful supporting resources include the medical billing concepts guide, AMBCI's Medicaid reimbursement calculator and guide, the physician fee schedule reimbursement guide, and the directory of billing solutions for small practices. These resources help connect coding decisions with claims, payment, and operational consequences.
-
Start with universal coding foundations, then gradually shift practice toward documentation and code families relevant to the specialty. Someone considering risk adjustment as a first specialty should develop strong diagnosis-documentation reasoning. Someone aiming for inpatient coding needs a different progression from someone targeting professional-fee coding.
You can also compare the longer-term earning and advancement potential across medical coding specialties before deciding where to place advanced study time.
-
Readiness should come from repeated evidence. You should be reaching your target accuracy on mixed, timed, unfamiliar questions, maintaining performance across delayed retests, navigating your allowed references efficiently, and explaining why difficult answers are correct.
Use a full CPC first-attempt preparation framework, test yourself with detailed CPC practice questions, and complete an exam-day readiness checklist. Readiness is strongest when good scores continue even after question order, examples, and testing conditions change.
